
What can a TENS response tell you about the bite?
Transcutaneous electrical nerve stimulation (TENS) has been studied for pain and muscle-activity changes in temporomandibular disorders (TMDs). A change after stimulation does not, by itself, identify the jaw position for definitive restorations or prove that a digital bite record is more accurate. The useful question is what each measurement can support in the patient in front of you. Controlled trial; evidence review.
Introduction
TMDs involve the jaw joints, masticatory muscles or both. Pain, restricted movement and a restorative problem may coexist, but they are not interchangeable diagnoses. Assess the presenting complaint before choosing a recording method. NIDCR overview.
In some neuromuscular workflows, TENS is used before recording muscle activity or mandibular position. The resulting record describes a response under those test conditions. It should not be labelled the patient’s uniquely correct or optimal bite. Monaco et al.; Sadek et al..
Digital occlusal records may include intraoral surface scans, registered jaw relationships and sensor recordings. These are different measurements: a scan-based contact display is not the same as a recording of bite-force timing. Scanner contact study; sensor measurement description.
For full-mouth rehabilitation, keep two questions separate: what was recorded, and whether using that record improves the planned treatment. The TENS studies discussed below do not establish that short-term muscle changes improve definitive restorative outcomes.
TENS: the measured response and its limits
What is TENS?
TENS delivers electrical impulses through electrodes placed on the skin. It has been studied for pain-related outcomes and muscle-activity changes. The masticatory muscles involved in jaw movement include:
- Masseter muscle: The primary muscle used for chewing.
- Temporalis muscle: Involved in closing the jaw.
- Pterygoid muscles: Important for jaw movements such as lateral and forward motion.
Surface electromyography (sEMG) records electrical activity from sampled muscles. A lower resting recording after TENS is a physiological observation; it is not a direct measurement of restoration fit or an instruction to change tooth contacts. Controlled trial.
What has actually been studied?
Keep pain, muscle activity, jaw position and restorative outcomes separate when interpreting a study:
- Pain Modulation: NIDCR reports possible pain relief and improved mouth opening in small TMD studies using short-duration TENS treatments. For adults with moderate chronic TMD pain lasting at least three months, a 2023 BMJ guideline conditionally recommends against TENS; that recommendation does not address acute TMD pain. NIDCR overview; BMJ guideline.
- Muscle activity: Monaco et al. studied a single 60-minute TENS session in 60 young women with unilateral TMD in remission. Resting muscle activity and interocclusal distance changed. The study did not test the accuracy of a definitive restorative jaw position. Study details.
- Pain sensitivity: Ferreira et al. compared active and placebo TENS in 40 people with myofascial TMD. Measurements were immediate and at 48 hours; pain-intensity scores did not differ between groups at any assessment. Some pressure-pain-threshold and EMG findings differed. Randomized trial.
- Clinical meaning: Changes in laboratory or short-term physiological measures should not be presented as proof of faster healing, improved restoration survival or more accurate bite calibration. Those require their own clinical outcome studies.
Before using a post-TENS record
The following distinctions help prevent a measurement from becoming an unsupported treatment conclusion.
1. Rest position and restorative position
- What was measured? The Monaco study assessed resting interocclusal distance and muscle activity. Its findings do not establish that the recorded rest position should be transferred directly into definitive restorations.
- Occlusion and TMD: NIDCR notes that research does not support a bad bite as a cause of TMDs. There is insufficient evidence that treatments which permanently change the teeth or bite treat TMDs, and some may make symptoms worse. NIDCR guidance.
2. Bruxism assessment
- Assess the behaviour: Sleep and awake bruxism are distinct forms of masticatory muscle activity. Their assessment may use history, examination and appropriate instrumental recordings. An immediate post-TENS response does not demonstrate that bruxism has been prevented. International consensus.
3. TMD pain and function
- Match the evidence to the complaint: A pain score, mouth-opening measurement and EMG recording describe different outcomes. The short-term studies above do not establish prevention of recurrent TMD symptoms or correction of a causative bite problem.
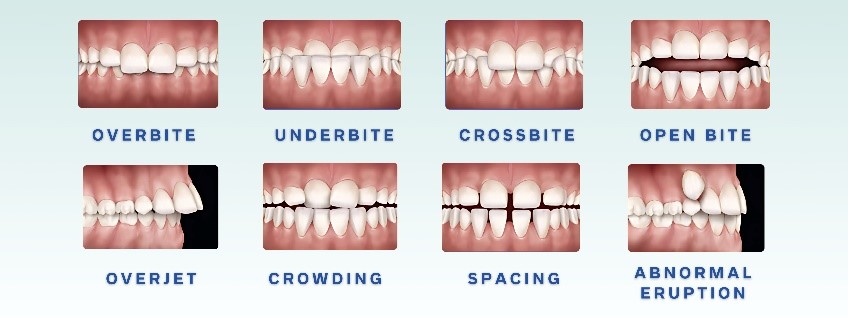
4. Orthodontic claims
- Tooth movement: Neither of these TENS trials tested whether braces or aligners work more effectively after stimulation. A muscle-activity change cannot be used as evidence of improved orthodontic alignment or stability.
- Comfort: A change in discomfort is a symptom outcome. It does not demonstrate more successful orthodontic tooth movement or justify a different orthodontic plan.
5. Restoration fit
- Keep the endpoint clear: The TENS trials did not test crown, bridge or denture fit. Muscle relaxation should not be presented as a guarantee that a restoration will fit correctly.
- After treatment: Short observation periods cannot establish fewer prosthetic complications or durable relief after full-mouth rehabilitation.
6. Patient experience
- Record the reported change: Pain relief matters to the patient. Report it as pain relief, with its timing and context, rather than as confirmation of an ideal occlusion.
- Separate the questions: Relief of symptoms and the suitability of a restorative plan need separate assessment. A favourable response to stimulation cannot answer both.
Where does TENS sit among TMD options?
- TENS: NIDCR describes possible short-term pain and mouth-opening benefits in small studies. This is different from establishing a dependable full-mouth rehabilitation protocol.
- Chronic TMD pain: The 2023 BMJ guideline favours several approaches, including supervised jaw exercise and stretching, manual trigger-point therapy and usual care such as education. Its recommendations concern pain lasting at least three months. Guideline.
- Scope matters: The guideline’s conditional recommendation against TENS is not a universal contraindication. It does not address acute TMD pain or validate TENS for restorative bite selection.
Questions to ask of a TENS-assisted workflow
- Accuracy: Was bite-registration accuracy measured against a suitable reference, or was only muscle activity measured?
- Patient benefit: Was there a meaningful between-group improvement in pain or function, rather than only a before-and-after change?
- Efficiency: Were treatment time and additional appointments actually measured? The trials above do not establish a faster restorative workflow.
- Durability: Was the patient followed after definitive treatment? Immediate or 48-hour measurements cannot demonstrate long-term restorative success.
Digital records in full-mouth rehabilitation
What is Full-Mouth Rehabilitation?
Full-mouth rehabilitation may involve restoring worn teeth or replacing missing teeth across an arch. TENS-related pain or EMG findings should not be treated as evidence that a particular restoration design or mandibular position is correct.
Digital records can support planning, but adding a TENS step does not automatically improve their accuracy. Keep the evidence for the recording method separate from the evidence for stimulation.
What does each digital record show?
Distinguish surface geometry, anatomical imaging, observed movement and sensor data before combining them in a treatment plan.
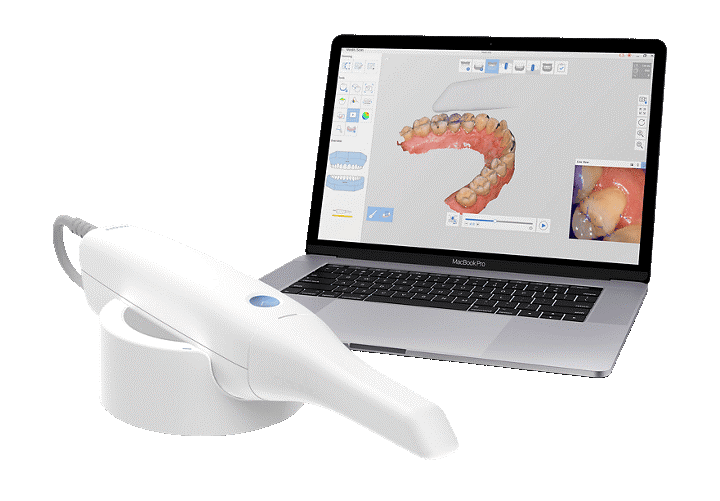
- Intraoral scans: These capture surface geometry and can be used to register the relationship between arches. Scanner contact displays should not be assumed to reproduce conventional contact markings exactly. Prospective contact-recording study.
- Radiographs: Anatomical imaging is a separate record from a bite-force or muscle-activity measurement; it does not establish the success of a TENS-assisted jaw record.
- Photography and video: These may document appearance and observed movement. They are not, by themselves, measurements of occlusal force or proof of a treatment benefit.
3D Modeling
- Digital impressions produce surface models; the interarch relationship depends on the registered bite. The prospective scanner study found differences between digital and photographed articulating-paper contact records. Do not interpret a convincing model display as proof that every contact is correct. Study.
- A model can be rotated and inspected on screen. That visualization does not demonstrate how the patient will function after definitive treatment.
Occlusal Force Distribution
- Sensor recordings: Systems such as T-Scan provide bite-sequence force and timing information. This is a device function, not independent evidence that using the system with TENS improves rehabilitation outcomes. Manufacturer description of the measurement.
Interpreting an apparent contact problem
- Record versus diagnosis: A contact pattern or jaw relationship is part of the assessment. It does not, on its own, explain the cause of TMD pain.
- Before changing the bite: NIDCR finds insufficient evidence for permanent occlusal changes as TMD treatment, with possible worsening in some cases. Keep this distinct from managing a separately established restorative problem. Occlusal-treatment guidance.
Treatment Planning
- Use digital displays to communicate the proposed restorative work and its assumptions. The evidence reviewed here does not establish that a TENS-derived position improves the result.
- Simulation: A simulated outcome is a planning display. It should not be presented to the patient as an observed result or a guarantee.
Follow-Up
- Compare the relevant clinical outcomes with the original treatment goals. A new scan or muscle recording answers a different question from a patient’s pain, comfort or function.
- Digital records do not establish that fewer physical follow-up visits are safe or sufficient. The TENS trials discussed here did not test that claim.
Does TENS validate bite calibration?
No definitive restorative-position validation follows from the short-term findings described above. In the 2026 evidence map, six studies used heterogeneous protocols and outcomes; the authors describe physiological and functional signals while calling for better-controlled research. Evidence map.
For the dentist, the distinction is practical: report the observed response, identify what the recording measures, and avoid promising an optimal bite, fewer adjustments or greater longevity unless those outcomes have been demonstrated.
What clinical evidence would support a rehabilitation claim?
A useful report would identify the diagnosis, restorative intervention, comparator where relevant, measured outcomes and follow-up. Combining TENS and digital tools is not itself evidence that pain relief was caused by correcting the bite.
The studies cited here do not establish a full-mouth rehabilitation success rate or long-term relief from a TENS-selected restorative position. Individual symptom changes should not be generalized into a promise of predictable rehabilitation.
Conclusion
Transcutaneous Electrical Nerve Stimulation (TENS) may alter resting muscle activity and mandibular position. These physiological changes do not, by themselves, establish the accuracy of digital occlusion analysis or the best restorative jaw position. A small controlled study measured immediate muscle-activity and interocclusal-distance changes after TENS, without assessing full-mouth rehabilitation outcomes. Monaco et al., 2013.
A 2026 systematic review found limited evidence for TENS/EMG-guided mandibular positioning and uncertainty about long-term occlusal stability and prognosis. These recordings should complement clinical assessment, rather than be assumed to guarantee better rehabilitation outcomes. Sadek et al., 2026.
References
- Clinical guidance: NIDCR: Temporomandibular Disorders; Busse et al. (2023), BMJ clinical practice guideline.
- TENS studies and evidence map: Monaco et al. (2013), controlled clinical trial; Ferreira et al. (2017), randomized placebo-controlled trial; Sadek et al. (2026), systematic review and evidence map.
- Assessment and digital measurements: Lobbezoo et al. (2018), international bruxism consensus; Prospective study of scanner and articulating-paper contact records (2024); Tekscan: bite timing measurement, manufacturer description.