
Zirconia vs Ceramics in Modern Dentistry: A Comprehensive Comparison
Which ceramic fits the restoration you are planning? Zirconia is itself a ceramic, so the useful comparison is between a specified zirconia and a specified glass-ceramic or porcelain, in a defined restoration. The choice should connect the tooth or implant support, available space, aesthetic objective, bonding plan and permitted indication. A laboratory strength value alone cannot tell a patient how long a crown will last.
DDS brings these distinctions together as a practical selection workflow for dentists and dental technicians. The studies below answer different questions: material testing explains properties, clinical studies describe outcomes in their enrolled patients, and manufacturers’ instructions define how a particular product may be used.
Start with the material and the restoration design
The classification proposed by Gracis and colleagues separates glass-matrix, polycrystalline and resin-matrix materials. Feldspathic porcelain, leucite-reinforced glass-ceramic and lithium disilicate should not be collapsed into one uniform “traditional ceramic” category. Zirconia belongs to the polycrystalline group. Zirconia-reinforced lithium silicate remains a glass-ceramic; the word zirconia in its description does not make it equivalent to a zirconia crown.
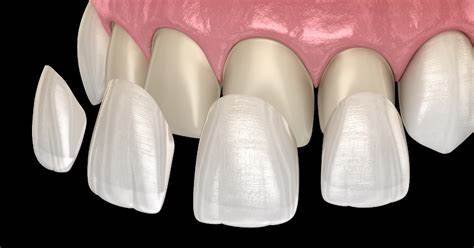
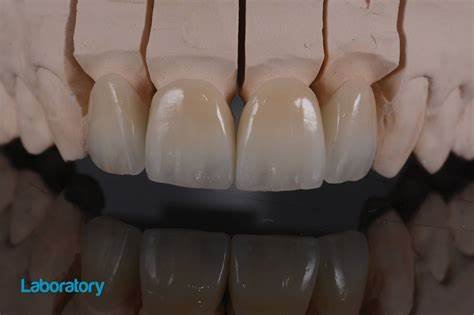
Then specify whether the restoration is monolithic, partly veneered or a veneered framework. In a monolithic crown, the main crown form is made from one ceramic; a layered restoration introduces a separate veneering ceramic. A veneer, tooth-supported crown, bridge and implant-supported crown are also different clinical applications. Evidence for one of them should not be silently transferred to another.
What does higher strength actually tell you?
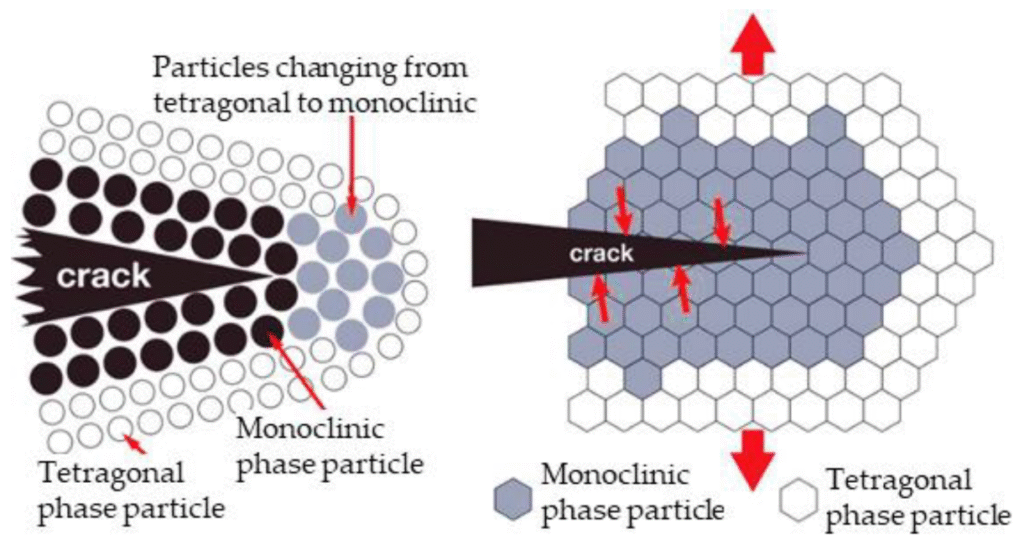
Zirconia composition matters. Labels such as 3Y, 4Y and 5Y refer to approximate yttria content in mol%, not interchangeable weight percentages. Changes in composition and phase balance affect translucency and mechanical behaviour. Transformation toughening involves stress-induced change of suitable tetragonal grains, with local expansion and energy absorption that can resist damage; it does not seal a crack or repair a fractured crown. The materials-science explanation by Zhang and Lawn describes this mechanism and its limitations.
A laboratory experiment by Yan, Kaizer and Zhang compared lithium disilicate with 3Y-, 4Y- and 5Y-zirconia using discs bonded to a dentin-like substrate. The lithium-disilicate system carried loads similar to the tested 4Y system and higher than the tested 5Y system; the 3Y system carried the highest loads. These were controlled fracture tests of bonded specimens, not follow-up of patients. The useful lesson is to examine the support, thickness and bonding conditions behind a mechanical comparison rather than apply one “zirconia is stronger” ranking to every restoration.
What can clinical survival evidence support?
In the three-year randomized trial reported by Le and colleagues, 71 patients received 90 posterior tooth-supported crowns: high-translucency zirconia, zirconia with a partial buccal veneer, or lithium disilicate. At three years, 66 patients with 84 crowns were examined. No crown fractures were reported during observation; retention and endodontic events still occurred. The groups did not differ significantly in the reported marginal-integrity, surface or anatomical-form assessments, and both patients and dentists rated aesthetics favourably.
This supports the use of several materials in the studied setting, not a universal five-year winner. Keep survival, complications and patient satisfaction separate. A crown can remain in service after an intervention, and a short-term result does not establish performance in a different zirconia grade, severe parafunction, a long-span bridge or an implant-supported reconstruction. Those distinctions should also shape the prognosis discussed with the patient.
Plan appearance with the underlying tooth in view
Translucency is one part of appearance. In Kim’s laboratory study, the tested higher-yttria zirconias were more translucent than the lower-yttria specimens, but remained less translucent than the tested lithium-disilicate materials. These were controlled optical measurements, not a demonstration that every patient prefers one material. A separate specimen study of thickness and resin cement found that both affected final colour and translucency.
For the clinical try-in, assess the prepared-tooth shade, masking requirement, intended thickness and selected cement together. A highly translucent option may be unsuitable when a dark substrate needs masking. Communicate the substrate and desired characterisation to the laboratory before manufacture; do not assume that a material-family name alone determines a natural result.
Check the exact product before treating high-load cases
Bruxism is a reason to investigate the restoration’s indication and the patient’s risk, not an automatic instruction to select any high-translucency zirconia. For example, the January 2025 KATANA Zirconia STML instructions, English page 2 advise against use with malocclusion, clenching or bruxism and prohibit four-unit-or-longer bridges and cantilevers. These restrictions apply to that product; they are not a statement that all zirconias share the same indications.
The same instructions specify restoration-dependent thickness and connector requirements. Do not transfer a single minimum thickness from a case description to all crowns, or infer that every zirconia permits less tooth reduction. If the planned geometry or clinical condition falls outside the selected product’s instructions, reconsider the product or restoration design before fabrication.
Bonding and surface finish are part of the material choice
Ivoclar’s material-conditioning guidance explains why glass-ceramics and zirconia use different adhesive pretreatments: glass-ceramic pathways use an appropriate etching/silane approach, whereas zirconia pathways use material-compatible airborne-particle abrasion and suitable phosphate-monomer chemistry. A universal primer does not make the preceding surface preparation universal. Match the restoration, primer and cement instructions, including cleaning after try-in and safety precautions. This overview is not a substitute for a complete cementation protocol.
For the opposing tooth, surface condition matters. A 12-month clinical comparison of glazed and polished monolithic zirconia crowns found greater opposing-enamel wear in the glazed group at the final recall. Separately, a randomized one-year study of 30 patients found comparable enamel wear with polished monolithic zirconia, metal-ceramic crowns and enamel controls. These different designs do not establish that one ceramic always wears enamel more or less than another.
The clinical implication is to inspect and finish adjusted contact surfaces using the chosen system’s instructions, then assess the restoration and opposing dentition during review. A crown’s hardness or glossy appearance alone is not enough to predict antagonist wear.
Use product names precisely in the prescription
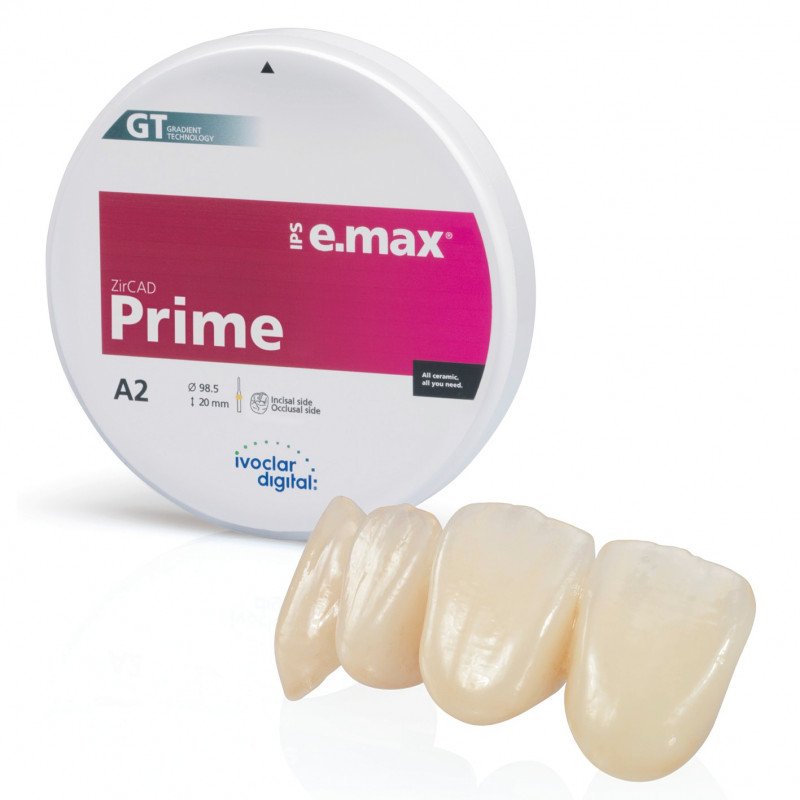
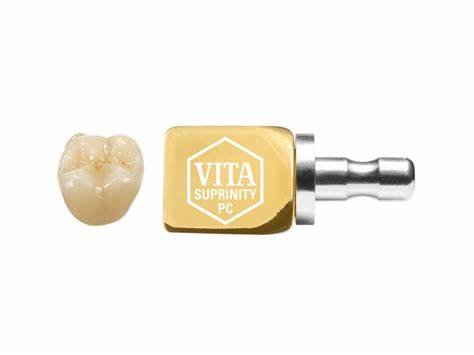
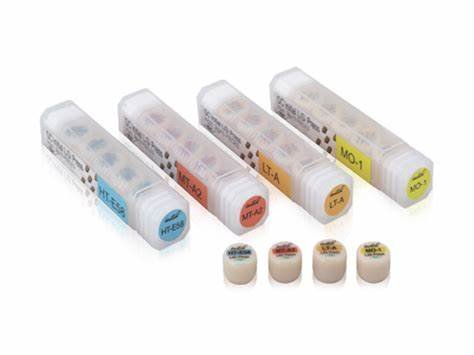
The examples below show why the complete product identity matters. They identify material families and supply formats, rather than rank brands. Confirm the exact grade, manufacturing route, compatible equipment and current local instructions with the laboratory; related products can have different indications.



Two clinical decisions to work through
Teaching example: a posterior crown with a history of fracture. First investigate the previous failure and assess support, available space and occlusal risk. Compare eligible products for that crown design, rather than assuming that a higher laboratory strength will prevent another failure. The STML restriction above demonstrates why the exact product must be checked before applying a general zirconia recommendation.
Teaching example: an anterior veneer with a demanding shade match. Establish the desired shape and colour change, the available enamel/substrate and the feasible restoration thickness. Select the optical and bonding system together. The specimen findings above help explain what to evaluate; they do not predict an individual patient’s aesthetic satisfaction or a veneer’s survival. These examples illustrate decisions, not reported patient treatments or follow-up outcomes.
Clinical takeaway
- For the dentist: define the restoration and patient constraints, then compare clinical evidence for that indication. Discuss complications and maintenance as well as survival; no material family guarantees a fracture-free result.
- For the laboratory: confirm the complete material grade and monolithic/veneered design, check geometry against its instructions, and communicate any incompatibility before manufacture. Do not substitute one family member’s thickness or processing cycle for another’s.
- At delivery and review: follow the selected conditioning and cementation system, inspect fit and adjusted surfaces, and review biological and technical findings. Investigate a problem rather than assuming a material substitution alone will solve it.
These are educational implications of the study designs and product constraints discussed above. The better choice is the material-restoration combination that meets the case requirements and can be fabricated, bonded or cemented, finished and maintained appropriately.
References
- Gracis S, Thompson VP, Ferencz JL, Silva NRFA, Bonfante EA. A new classification system for all-ceramic and ceramic-like restorative materials. Int J Prosthodont. 2015;28:227–235. DOI: 10.11607/ijp.4244. Publication record.
- Zhang Y, Lawn BR. Novel Zirconia Materials in Dentistry. J Dent Res. 2018;97:140–147. DOI: 10.1177/0022034517737483. Full text.
- Yan J, Kaizer MR, Zhang Y. Load-bearing capacity of lithium disilicate and ultra-translucent zirconias. J Mech Behav Biomed Mater. 2018;88:170–175. DOI: 10.1016/j.jmbbm.2018.08.023. Publication record.
- Le M, Dirawi W, Papia E, Larsson C. Clinical Outcome of Three Different Types of Posterior All-Ceramic Crowns. A 3-Year Follow-up of a Multicenter, Randomized, Controlled Clinical Trial. Int J Prosthodont. 2023;36:546–553. DOI: 10.11607/ijp.8016. Publication record.
- Kim HK. Optical and Mechanical Properties of Highly Translucent Dental Zirconia. Materials. 2020;13:3395. DOI: 10.3390/ma13153395. Publication record.
- Influence of Restoration Thickness and Resin Cement on Translucency and Color of Different Types of Monolithic Zirconia and Lithium Disilicate Ceramic. PubMed record, PMID 36971621. In-vitro study.
- Comparative Evaluation of Wear of Natural Enamel Antagonist Against Glazed Monolithic Zirconia Crowns and Polished Monolithic Zirconia Crowns: An In Vivo Study. PubMed record, PMID 35998079.
- Esquivel-Upshaw JF, et al. Randomized clinical study of wear of enamel antagonists against polished monolithic zirconia crowns. J Dent. 2018;68:19–27. DOI: 10.1016/j.jdent.2017.10.005. Publication record.
- Kuraray Noritake Dental. KATANA Zirconia STML instructions for use, 012 TI-012-EN, January 2025. English page 2. Accessed 14 October 2026. Use the current version applicable to the product and country.
- Ivoclar. Pre-treatment of restorations before adhesive cementation. Manufacturer guidance, accessed 14 October 2026. Product-identification links are also supplied with the relevant figures.