
Wear resistance of contemporary composite materials: evidence and clinical decisions
Composite wear is a loss of material under interacting mechanical and chemical conditions. It matters for contour, contacts and maintenance, but a wear measurement is not a restoration-survival estimate. Choose a restorative system for the tooth, preparation, opposing surface and patient, then follow its instructions for placement, bonding and polishing. Neither a “nano” label nor industrial polymerization guarantees the longest clinical service.
Learning objectives
After reading, you should be able to:
- Describe the mechanical and chemical factors involved in composite wear, distinguishing restorative-material loss from opposing-tooth wear.
- Compare wear-test conditions and measurement endpoints without treating laboratory cycles as clinical years.
- Distinguish laboratory material-property evidence from clinical restoration success, survival, repair and replacement outcomes.
- Identify the patient, restoration and product-specific checks that guide material selection, finishing and maintenance.
What wears, and how?
Two-body abrasion involves direct contact between surfaces; three-body abrasion includes an intervening abrasive medium. Repeated loading can contribute to fatigue damage and particle loss. Chemical exposure and water can alter the resin matrix or filler interface and interact with mechanical loading. In natural teeth, attrition, abrasion and erosive tooth wear describe related but distinct processes. Enamel dissolution should not be treated as identical to polymer degradation. The original biodegradation study by de Paula and colleagues tested restorative materials experimentally, rather than measuring patients’ annual wear. [de Paula]
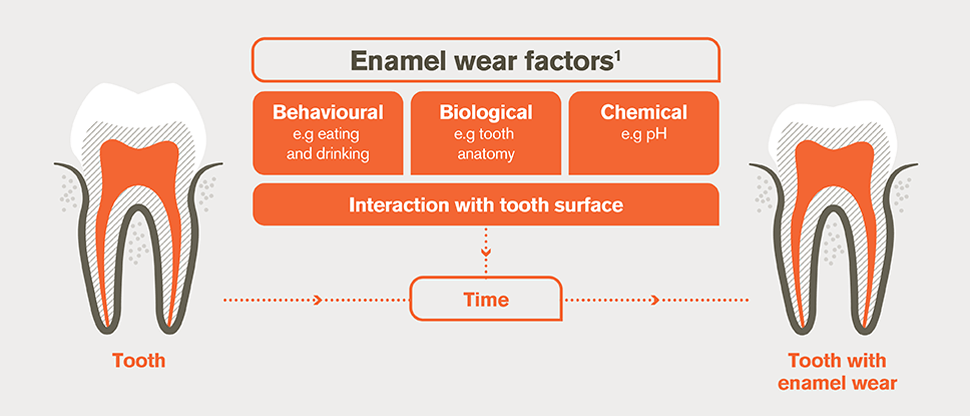
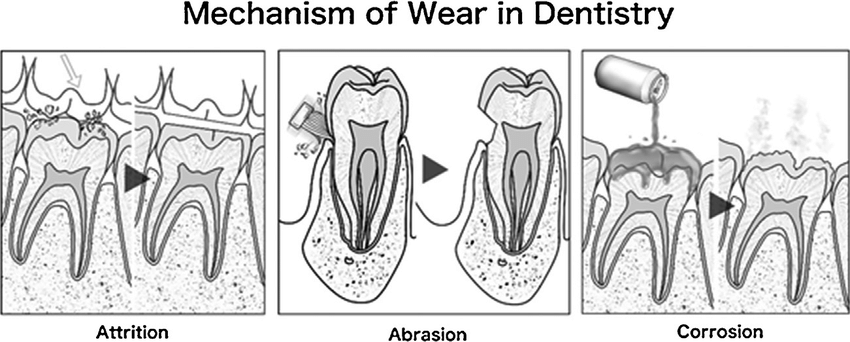
Force, contact geometry, sliding, antagonist roughness, lubrication, exposure time and chemical conditions all matter. A high force in one test does not reproduce every aspect of bruxism. The worn restoration and its opposing tooth must be assessed separately: low material loss can coexist with appreciable antagonist wear. D’Arcangelo and colleagues’ ceramic–enamel comparison is laboratory evidence, not a clinical ranking of all composites. [D’Arcangelo]
Composition is a starting point, not a league table
Matrix chemistry, conversion, filler loading and distribution, filler–matrix coupling, porosity and surface treatment work together. Bis-GMA-, UDMA-, silorane- and organically modified ceramic systems cannot be ranked clinically from monomer names alone. Smaller particles may help some surface properties, but size and filler percentage do not by themselves establish wear resistance. Ferracane’s analysis and the Academy of Dental Materials guidance distinguish laboratory material properties from the clinical outcomes they are sometimes asked to predict. [Ferracane] [Ilie]
- Microhybrid, nanohybrid and nanofilled direct composites: these labels describe aspects of formulation, not universal annual wear rates. Select products indicated for the intended restoration, supported by relevant evidence and a feasible curing protocol.
- Bulk-fill composites: allowable increment depth and any required occlusal capping layer are product-specific. “Flowable” does not automatically mean every product needs the same cap, and “bulk-fill” does not authorize an arbitrary 4–5 mm increment under every light or shade.
- Fiber-reinforced composites: coverage and the intended core or surface application matter. For example, GC specifies everX Posterior as dentin replacement covered with light-cured restorative composite; it is not an exposed surface layer. Fracture reinforcement should not be presented as proof of lower occlusal wear. [everX Posterior]
- CAD/CAM resin composites and polymer-infiltrated ceramic networks: these are not interchangeable structures. VITA Enamic is a polymer-infiltrated ceramic network; Lava Ultimate is a resin-matrix material containing ceramic fillers. Processing, machinability and reparability need to be considered alongside bonding and clinical indication. [Ruse and Sadoun]


Low-shrinkage chemistry is also a different endpoint: Kruly and colleagues’ meta-analysis concerns clinical behavior of low-shrinkage versus methacrylate restorations, not a universal wear advantage for a matrix class. Johnsen and colleagues examined own-brand restorative materials; brand category alone is not a clinical wear specification. [Kruly] [Johnsen]
Read the test before comparing the number
Two-body and three-body simulators, toothbrush tests and thermomechanical aging impose different conditions. Report the product, antagonist, load, cycles, medium, aging, surface preparation and measurement method. Maximum vertical loss, average depth, volume loss, roughness and gloss are different endpoints. A surface can become smoother while losing material. Laboratory cycles must not be converted into clinical years without a validated relationship.
Barkmeier and colleagues explicitly compared localized and generalized simulated wear. Heintze and colleagues reviewed the relationship between laboratory mechanical parameters and clinical fractures and wear; laboratory results do not provide a general replacement for clinical follow-up. Nawafleh and colleagues’ fatigue review concerned lithium-disilicate crowns and fixed prostheses, with heterogeneous test setups, rather than composite annual wear. [Barkmeier] [Heintze] [Nawafleh]
Clinical evaluation combines symptoms, function, margins, fracture and caries assessment with serial records. FDI or USPHS ratings are clinical scores, not direct micrometre measurements. Serial scans or casts need reproducible acquisition, stable registration regions and a stated uncertainty before differences are interpreted as progression. Passos and colleagues compared measurement methods on experimentally eroded or abraded enamel and dentin; their findings cannot simply be transferred to clinical composite wear. [Passos]
What the retained evidence actually shows
Laboratory CAD/CAM wear
Zhi, Bortolotto and Krejci’s 2016 experiment tested five CAD/CAM materials, with 10 specimens per material, against human enamel cusps. It used 200,000 mechanical cycles at 49 N with thermal cycling and assessed maximum vertical substance loss. The tested feldspathic ceramic, VITA Mark II, resisted wear better than the tested resin-containing blocks. This was not a direct-versus-indirect clinical trial and did not establish annual clinical wear rates, patient survival, or a universal ranking of CAD/CAM materials. [Zhi]
Matzinger and colleagues’ 2019 laboratory study compared polishing, specimen wear and antagonist wear across seven chairside CAD/CAM materials. Material ranking depended on whether mean depth, maximum depth or volume was used. Its polished surfaces and wear simulation support careful finishing and endpoint-specific comparison, not a promise of fewer clinical remakes. [Matzinger]
Tsujimoto and colleagues’ 2017 experiment compared six CAD/CAM materials after water storage or 10,000 thermal cycles, followed by localized simulated wear. Aging effects varied by material and endpoint. Stawarczyk and colleagues’ mechanical and optical characterization is additional material-property evidence, not a clinical longevity trial. [Tsujimoto] [Stawarczyk]
Clinical restoration survival and maintenance
Loomans and colleagues’ 2018 prospective study treated 34 patients with severe tooth wear using 1,256 direct composite restorations. At a mean observation of 39.7 months, 69 failures were recorded: 61 restorations were repaired and eight replaced. Reported 3.5-year success and survival were 94.8% and 99.3%, respectively. Those distinct figures reflect the importance of repair in the outcome definition. This study supports the feasibility of a direct composite rehabilitation strategy in its setting; it does not compare direct nanofill against CAD/CAM blocks or provide category-wide micrometres per year. [Loomans]
Borgia and colleagues’ retrospective posterior-restoration study adds long-term clinical observation, but its design and population differ from the laboratory comparisons and the full-mouth rehabilitation cohort. Neither source justifies prescribing one material for every patient who reports grinding. [Borgia]
A practical workflow for a worn posterior restoration
Illustrative decision pathway, not a reported patient case. When a patient presents with worn restorations and possible parafunction, document the history, symptoms, remaining tooth structure, opposing surfaces, margins, caries and functional contacts. Determine whether repair, replacement or broader rehabilitation is needed. Wear facets or a history of grinding alone do not establish the cause of every defect or quantify loss of vertical dimension.
- Establish a baseline. Record photographs, clinical scores and, where useful, digital scans. Document the intended follow-up method and measurement limitations before comparing later scans.
- Select the restoration and material together. Consider available space, retention, bondable substrate, isolation, restoration thickness, antagonist and reparability. Direct composite and an indicated indirect onlay can both be options; this is not a controlled within-patient material comparison.
- Use conservative preparation and reliable isolation. Preserve sound structure, obtain appropriate access and follow the chosen material’s preparation and adhesive instructions.
- Respect the specific bonding system. Scan, design, mill and try in an indirect restoration as appropriate; verify contacts and fit before surface pretreatment. Do not apply a single generic silane-plus-adhesive sequence to every resin-containing block.
- Place and cure direct composite to its instructions. For a product such as Filtek Supreme Ultra, use its current shade-, increment- and light-specific directions. An extra 20 seconds from each side is not a universal validated curing prescription. Check light output, access and tip position rather than relying on time alone.
- Finish, adjust and repolish. Check contacts and occlusion clinically and use the material’s polishing system. Do not add heat treatment or firing unless the specific system permits it.
- Plan maintenance. Reassess causes and progression, discuss appropriate protection where indicated, and document repairs separately from replacements. A protective appliance does not guarantee wear prevention or establish a material’s superiority. Irreversible occlusal equilibration is not a routine requirement inferred from grinding alone.
Lava Ultimate: retain the product-specific safeguards
The manufacturer’s 2015 instructions specify inlays, onlays and veneers and exclude crowns because of debonding risk. Onlays require an internal retentive design element; the term “overlay” alone does not establish that a preparation meets the indication. The instructions describe alumina abrasion at no more than 50 μm and 2 bar, alcohol cleaning and dry, oil-free air. They prohibit HF or phosphoric-acid etching of the restoration. For the RelyX Ultimate/Scotchbond Universal combination, the adhesive acts as primer; other cements require their recommended priming sequence. The block must not be fired. These instructions are product-specific and must be checked against the current local package directions before use. [Lava Ultimate instructions]
Research directions and the clinical bottom line
When evaluating proposed self-healing polymers, bioactive fillers, modified networks or computationally designed materials, ask which properties and outcomes were actually tested. A laboratory improvement in hardness, strength, conversion or gloss is not automatically a demonstrated reduction in patient wear, fracture, repair or replacement. Emerging chemistry needs biocompatibility, processing and clinical evaluation as well as wear testing.
The retained evidence does not support a universal annual wear-rate table for the broad categories used here. Compare like-for-like tests, retain the distinction between restorative and antagonist wear, and assess clinical survival separately. Product-specific technique, patient assessment and planned maintenance remain central to a useful treatment decision.
References and product documentation
References (19)
- Barkmeier WW, Takamizawa T, Erickson RL, Tsujimoto A, Latta M, Miyazaki M. Localized and generalized simulated wear of resin composites. Oper Dent. 2015;40(3):322–335. Source
- Borgia E, Baron R, Borgia JL. Quality and survival of direct light-activated composite resin restorations in posterior teeth: A 5- to 20-year retrospective longitudinal study. J Prosthodont. 2019;28(1):e195–e203. Source
- de Paula AB, Fucio SBP, Ambrosano GMB, Alonso RCB, Sardi JCO, Puppin-Rontani RM. Biodegradation and abrasive wear of nano restorative materials. Oper Dent. 2011;36(6):670–677. Source
- D’Arcangelo C, Vanini L, Rondoni GD, De Angelis F. Wear properties of dental ceramics and porcelains compared with human enamel. J Prosthet Dent. 2016;115(3):350–355. Source
- Ferracane JL. Resin-based composite performance: Are there some things we can’t predict? Dent Mater. 2013;29(1):51–58. Source
- Heintze SD, Ilie N, Hickel R, Reis A, Loguercio A, Rousson V. Laboratory mechanical parameters of composite resins and their relation to fractures and wear in clinical trials: A systematic review. Dent Mater. 2017;33(3):e101–e114. Source
- Ilie N, Hilton TJ, Heintze SD, Hickel R, Watts DC, Silikas N, Stansbury JW, Cadenaro M, Ferracane JL. Academy of Dental Materials guidance: Resin composites: Part I: Mechanical properties. Dent Mater. 2017;33(8):880–894. Source
- Johnsen GF, Thieu MKL, Hussain B, Pamuła E, Reseland JE, Lyngstadaas SP, Haugen H. Own brand label restorative materials: A false bargain? J Dent. 2017;56:84–98. Source
- Kruly PC, Giannini M, Pascotto RC, Tokubo LM, Suga USG, Marques ACR, Terada RSS. Meta-analysis of the clinical behavior of posterior direct resin restorations: Low polymerization shrinkage resin in comparison to methacrylate composite resin. PLoS One. 2018;13(2):e0191942. Source
- Loomans BAC, et al. Clinical performance of full rehabilitations with direct composite in severe tooth wear patients: 3.5 Years results. J Dent. 2018;70:97–103. Source
- Matzinger M, Hahnel S, Preis V, Rosentritt M. Polishing effects and wear performance of chairside CAD/CAM materials. Clin Oral Investig. 2019;23(2):725–737. Source
- Nawafleh N, Hatamleh M, Elshiyab S, Mack F. Lithium Disilicate Restorations Fatigue Testing Parameters: A Systematic Review. J Prosthodont. 2016;25(2):116–126. Source
- Passos VF, Melo MAS, Vasconcellos AA, Rodrigues LKA, Santiago SL. Comparison of methods for quantifying dental wear caused by erosion and abrasion. Microsc Res Tech. 2013;76(2):178–183. Source
- Ruse ND, Sadoun MJ. Resin-composite blocks for dental CAD/CAM applications. J Dent Res. 2014;93(12):1232–1234. Source
- Stawarczyk B, Liebermann A, Eichberger M, Güth JF. Evaluation of mechanical and optical behavior of current esthetic dental restorative CAD/CAM composites. J Mech Behav Biomed Mater. 2016;55:1–11. Source
- Tsujimoto A, Barkmeier WW, Takamizawa T, Latta MA, Miyazaki M. Influence of Thermal Cycling on Flexural Properties and Simulated Wear of Computer-aided Design/Computer-aided Manufacturing Resin Composites. Oper Dent. 2017;42(1):101–110. Source
- Zhi L, Bortolotto T, Krejci I. Comparative in vitro wear resistance of CAD/CAM composite resin and ceramic materials. J Prosthet Dent. 2016;115(2):199–202. Source
- 3M ESPE. Lava Ultimate CAD/CAM Restorative. Instructions for use, 2015 revision (06032015 V7). Manufacturer-authored document hosted by ProCAD Dental; verify current local package instructions. Source
- GC. everX Posterior: product indications and instructions. Dentin-replacement material requiring a covering composite layer. Source
About Dr. Haitham Sharshar



Dr. Haitham Sharshar is an international digital dentistry speaker, educator, and digital occlusion consultant based in Cairo, Egypt. His work focuses on functional digital dentistry, CAD/CAM, implantology, jaw-motion analysis, and the integration of digital diagnostics into clinical treatment planning.
As Founder and Scientific Coordinator of Digital Dentistry Schoology (DDS), he has trained more than 3,270 dentists and dental technicians through university programs, international conferences, and hands-on courses. His teaching connects patient-specific diagnostic records with digital design and clinical workflows, helping clinicians and technicians understand how function and occlusion inform restorative planning.
Dr. Sharshar is a certified trainer for zebris JMA-Optic+ jaw-motion analysis and MyoWise dental EMG. His educational and consulting work brings together patient diagnostics, jaw-motion records, muscle-activity data, digital occlusion, and AI-supported workflows.
He is Founder and Clinical Director of Occlusa, an AI-supported platform for organizing clinical information and supporting clinician-led review and treatment planning. He also owns HS Dental Clinic in Cairo, where his clinical focus includes full-mouth digital rehabilitation and smile design.
His speaking and training topics include functional digital dentistry, digital occlusion, jaw-motion analysis, CAD/CAM workflows, digital implantology, and the practical integration of AI-supported tools into dental education and clinical practice.
WHERE DIGITAL MEETS CLINICAL
Happy to collaborate on spreading digital dentistry.
h.sharshar@ddschoology.com