
Orofacial Pain and Muscle Spasm: A Comprehensive Guide for Dental Practitioners
Orofacial pain and restricted jaw movement require a diagnosis before treatment. This guide separates acute problems after dental treatment from persistent temporomandibular disorder (TMD) pain and explains the limits of commonly discussed therapies. It is professional education, not a patient-specific prescription.
Executive summary
- Jaw pain, muscle tenderness and limited opening can have different causes. Do not assume every painful or restricted jaw represents muscle spasm.
- Assess the teeth, joints, muscles, pain history and functional impact; consider other causes when findings do not fit a TMD diagnosis.
- Use evidence matched to the condition and duration. A chronic-TMD guideline cannot be applied automatically to acute postoperative symptoms.
- Choose measurable goals and reassess both benefit and adverse effects rather than promising a fixed recovery time.
Introduction and diagnostic approach
Orofacial pain represents a challenging diagnostic and management scenario in dentistry. These conditions span acute dental pathology and persistent pain disorders with substantial effects on quality of life. The relationship between pain, muscle guarding and restricted movement often requires an interdisciplinary approach.
TMD describes conditions involving the temporomandibular joints and associated muscles. Facial pain can also arise from dental or other conditions, so history and examination come first. Imaging may be considered when clinically indicated; it does not replace the clinical assessment. [1]
Assess dental and periodontal disease, neuralgic or other neuropathic pain, and headache-related pain alongside musculoskeletal causes. When symptoms or examination findings do not fit a dental or TMD diagnosis, arrange an appropriate orofacial-pain, medical or neurological assessment rather than escalating jaw-focused treatment. [8]
The Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) combine a standardized physical assessment with evaluation of pain-related disability and psychosocial factors. For common pain-related TMD, the examination considers whether movement or palpation reproduces the patient’s familiar pain. Psychological distress is relevant to care without making pain imaginary or establishing a separate “psychogenic” cause. New sensory loss, weakness or unexplained swelling warrants assessment for another cause before conservative TMD care. [2]
A true masticatory muscle spasm involves an involuntary sustained contraction with sudden onset; soreness or restricted opening alone does not establish it. ICOP distinguishes spasm-related myofascial pain from other muscle-pain conditions and notes that its proposed criteria for these secondary disorders require further validation. [8]
Clinical applications: two distinct assessment pathways
Use the duration, trajectory and clinical findings to select the assessment pathway. Acute deterioration requires prompt exclusion of complications; persistent pain needs a broader review of function, contributing factors and previous treatment response.
Acute pain or limited opening after a dental procedure
- Reassess the cause. Record onset, progression, swelling, fever, the procedure performed and current medicines. Restricted opening is a finding, not proof that the problem is solely muscular. Suspected dental infection needs urgent dental assessment. [6]
- Identify urgent escalation. Breathing, speaking or swallowing difficulty, substantial mouth swelling, or eye swelling or visual disturbance requires emergency assessment. In a suspected dental abscess, marked difficulty opening the mouth is also an emergency warning. Use the local emergency service rather than waiting for routine review. [6]
- Match pain management to the diagnosis. For adolescents aged 12 years and older and adults, the ADA guideline supports nonopioid analgesia, particularly NSAIDs alone or with acetaminophen when appropriate, as first-line treatment for acute pain after extraction. This is an analgesia recommendation, not evidence that a particular drug regimen resolves muscle spasm or all causes of trismus. [5]
- Individualize follow-up. Explain expected progress, how to use any prescribed medicine, and when to return sooner. Worsening symptoms call for reassessment; recovery varies with the diagnosis and procedure.

Persistent or chronic TMD pain
The 2023 BMJ guideline concerns pain associated with TMD lasting at least three months and explicitly excludes acute TMD pain. Within that scope, it supports education/usual care, supervised jaw exercise and stretching, selected manual therapies, postural exercise, and cognitive behavioural therapy (CBT), with or without specified adjuncts. Treatment should be chosen with the patient and adapted to function and response. [3]
Document pain interference, eating and speaking limitations, sleep, relevant habits, and patient priorities. Repeated measures of pain and opening can help track progress, but a single change in millimetres or a percentage pain reduction does not prove which part of a multimodal treatment caused improvement. The DC/TMD framework includes both clinical findings and patient-reported impact. [2]
Treatment evidence and practical limits
Physical and behavioural care
Simple measures may include temporary food modification, reducing aggravating jaw habits, and clinician-guided heat or cold and gentle exercises. Many TMD symptoms improve without invasive treatment. Persistent or diagnostically uncertain symptoms warrant review. [1]
For chronic TMD, the BMJ panel strongly favoured CBT with or without biofeedback or relaxation, supervised exercise options, therapist-assisted mobilization and manual trigger-point therapy. Its recommendations do not establish a universal number of sessions, a guaranteed pain reduction, or prevention of chronic pain in an acute postoperative population. [3]
Medicines: evidence is not a universal prescription
A 2017 review by Häggman-Henrikson and colleagues evaluated medicines for adult chronic orofacial pain. It identified a cyclobenzaprine benefit signal for chronic muscle-related TMD, based on limited studies. The small evidence base does not establish routine use of muscle relaxants or a predictable individual response. [4]
For acute dental pain, review contraindications, concurrent medicines and the intended duration before selecting an analgesic. NSAIDs carry gastrointestinal, renal and cardiovascular risks; acetaminophen can cause liver injury and may be duplicated in combination products. The choice and instructions must fit the patient rather than a generic example. [5]
Diazepam is a benzodiazepine. FDA warnings describe risks including misuse, addiction, physical dependence and withdrawal; combining benzodiazepines with opioids or other central nervous system depressants can cause serious harm. A prescriber must assess risks and counsel the patient. Do not stop an established benzodiazepine abruptly without clinical advice. [7]
The BMJ panel conditionally recommended against benzodiazepines for chronic TMD pain. Its scope does not establish efficacy or appropriate prescribing for acute postoperative symptoms. [3]
Oral appliances and procedural options
Evidence that intraoral appliances improve TMD pain is limited. An appliance should not be intended to permanently alter the bite, and pain during use requires review. Tooth protection and TMD pain relief are different treatment goals. [1]
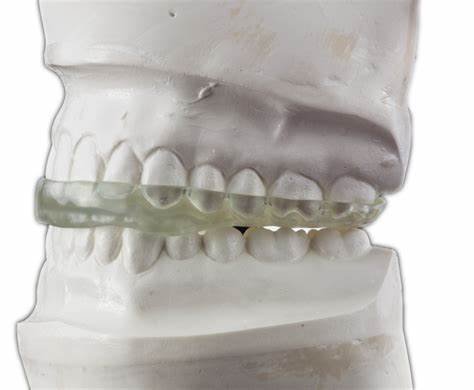
For chronic TMD pain, the BMJ guideline conditionally recommends against reversible occlusal splints and botulinum toxin injections compared with placebo or sham, and strongly against irreversible splints. These recommendations concern the specified pain population, not every possible dental indication. [3]
Botulinum toxin is not FDA-approved for TMD; findings on symptom relief remain mixed. Its benefits and risks require indication-specific specialist assessment. [1]
Putting conservative care into practice
- Agree on the main problem. Separate pain, restricted movement, tooth protection and other symptoms; a device selected for one goal may not address another.
- Choose a realistic functional target. For example, record which foods or daily activities are difficult and reassess that same task alongside pain and opening measurements.
- Explain the plan. Demonstrate any home exercise, document medicine instructions and make clear which symptoms require earlier review.
- Review rather than automatically escalate. Check adherence, benefit, adverse effects and whether the working diagnosis still fits. Seek specialist input when the diagnosis is uncertain or function remains substantially impaired.


Benefits, limitations and research priorities
A structured, multimodal approach keeps the patient’s function and participation central. Its limitations should also be explicit: evidence varies between treatments, different diagnoses should not be pooled indiscriminately, and group-average outcomes do not predict a guaranteed response.
When reviewing a new drug, device or injection study, check the diagnosis and symptom duration of the participants, comparator, adverse events, follow-up and patient-important outcomes. A pilot result or an imaging change alone is insufficient to establish routine clinical benefit.
Conclusion
Effective orofacial pain care starts with a defensible diagnosis and goals that matter to the patient. Distinguish urgent postoperative problems from chronic TMD, choose reversible and evidence-matched care, and review response and safety. No case anecdote, appliance image or numerical success claim can substitute for individual assessment.
References
- National Institute of Dental and Craniofacial Research. TMD (Temporomandibular Disorders). Reviewed September 2026. Diagnosis, conservative care, appliance and botulinum-toxin limitations.
- Schiffman E, Ohrbach R, Truelove E, et al. Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) for Clinical and Research Applications. Journal of Oral & Facial Pain and Headache. 2014;28(1):6–27. doi:10.11607/jop.1151.
- Busse JW, Casassus R, Carrasco-Labra A, et al. Management of chronic pain associated with temporomandibular disorders: a clinical practice guideline. BMJ. 2023;383:e076227. doi:10.1136/bmj-2023-076227. Scope: TMD pain lasting at least three months; excludes acute pain.
- Häggman-Henrikson B, Alstergren P, Davidson T, et al. Pharmacological treatment of oro-facial pain: health technology assessment including a systematic review with network meta-analysis. Journal of Oral Rehabilitation. 2017;44(10):800–826. doi:10.1111/joor.12539.
- American Dental Association. Acute dental pain management guideline and clinician resources (2024 adult/adolescent guideline; JADA doi:10.1016/j.adaj.2023.10.009); Oral Analgesics for Acute Dental Pain. Scope: acute extraction pain and temporary management of toothache, not all causes of trismus.
- NHS. Dental abscess. Reviewed 18 March 2026. Urgent assessment and emergency warning signs.
- U.S. Food and Drug Administration. FDA requiring Boxed Warning updated to improve safe use of benzodiazepine drug class. 23 September 2020.
- International Classification of Orofacial Pain, 1st edition (ICOP). Cephalalgia. 2020;40(2):129–221. doi:10.1177/0333102419893823.
Sources checked 14 October 2026.