

When an older patient struggles to chew, should you adjust the occlusion, improve denture support, or replace the prosthesis?
An older patient who struggles to chew may have an unstable denture, painful tissues, dry mouth, worn teeth, limited movement, or difficulty handling the prosthesis. An occlusal adjustment will not address all of these problems. The first task is to identify what is limiting this patient’s function and what they want treatment to achieve.
This article connects those findings to decisions about maintaining, adjusting, relining, or replacing a prosthesis, and explains when digital occlusal records can add useful information. The aim is comfortable everyday function and a result the patient can use and maintain. Age alone does not select an occlusal scheme or prescribe a change in vertical dimension.
1. Start with the patient’s functional problem
Ask which foods are difficult, whether pain or looseness interrupts meals, and what has changed since the prosthesis last worked comfortably. Establish how the patient inserts, removes, and cleans it, and whether help is available. Agree on a specific goal, such as eating a particular food more comfortably or reducing movement of a lower denture.
Record the complaint before collecting additional measurements. Schimmel et al. (2021) describe oral function as an interaction between biological capacity, learned skills, and the demands of daily life. That framework helps keep treatment focused on the patient’s difficulty rather than on a device reading alone.
2. Connect the examination to a treatment decision
Examine the remaining dentition, prosthesis fit and support, mucosa, salivary symptoms, jaw movement, and existing contacts. The assessment table below retains the individual factors that can change the plan. Findings must be established in this patient; they should not be assumed from age.
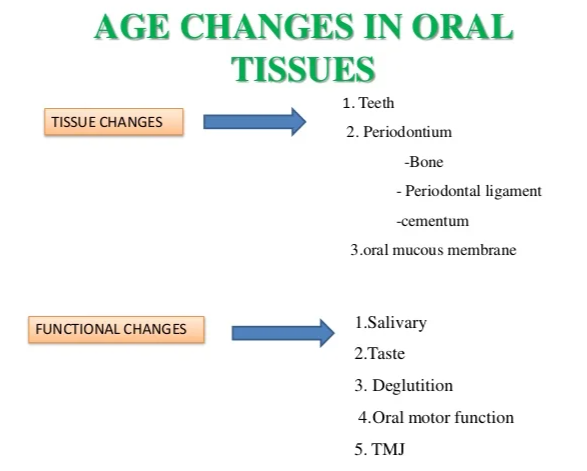
| Assessment domain | Finding to document | How it informs the plan |
|---|---|---|
| Neuromuscular function | Movement difficulty, fatigue, or limited control | Observe how the patient chews and handles the prosthesis; identify what the proposed treatment needs to make easier. |
| Contact perception | Difficulty identifying or describing an uncomfortable contact | Correlate the patient’s report with repeatable clinical findings before choosing an adjustment. |
| Muscle function | Variation in strength or endurance | Record the actual functional limitation and a baseline for review; do not infer a bite-force target from age. |
| Joint structures | Pain or restricted movement | Assess the symptoms and usable movement range before changing the occlusion or jaw relation. |
| Salivary function | Dry-mouth symptoms and relevant medication history | Include salivary assessment in the plan. Fortuna et al. (2023) found medication-associated differences in salivary flow in patients with xerostomia. |
| Communication and cognition | Support needed to understand instructions or report problems | Adapt communication and establish who can assist with use, hygiene, and review. |
| Oral mucosa | Tenderness, ulceration, or other tissue findings | Identify the cause and assess the denture-bearing tissues and fit before attributing discomfort to occlusion. |
For an existing removable prosthesis, distinguish a contact problem from loss of base adaptation, support, or retention. The American College of Prosthodontists (ACP) recommends assessing these features together with vertical dimension, speech, appearance, and satisfaction before deciding to reline, rebase, or remake it.
3. Match the intervention to the prosthesis and the problem
Complete dentures: establish support before choosing the scheme
If the main finding is poor base fit, evaluate whether a reline, rebase, or new denture is appropriate. If fit and support are acceptable but a reproducible contact discrepancy is present, assess whether a targeted occlusal correction addresses the complaint. Worn teeth, altered jaw relations, and multiple deficiencies may require a broader plan. These are clinical decision branches, not automatic prescriptions.
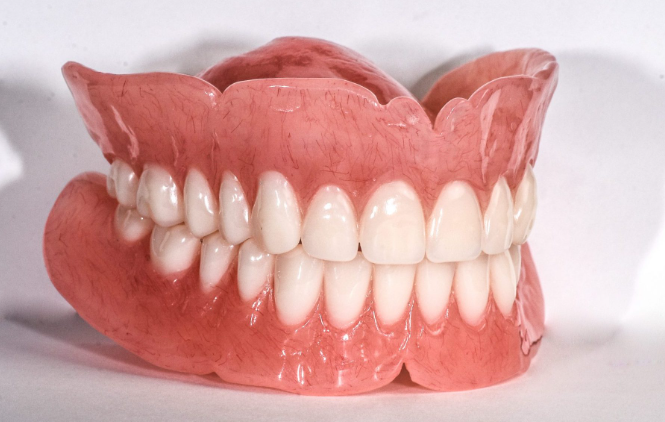
When new dentures or a new tooth arrangement are indicated, relate the scheme to the ridge condition, existing function, and treatment goals. In a 60-person randomized trial, Kawai et al. (2017) found no overall difference in the primary outcome between lingualized and fully bilateral balanced occlusion. A subgroup with severely resorbed mandibular ridges reported better retention and a more favorable pain-domain result with lingualized occlusion at six months. This supports considering lingualized occlusion in that clinical context, with appropriate caution about a subgroup finding.
A separate 60-person trial by Grech et al. (2022; published online in 2021) compared balanced, lingualized, and monoplane schemes over 52 weeks. Satisfaction and quality-of-life scores did not differ significantly between schemes, although fewer cases in the lingualized group required adjustment. Together, these studies support a reasoned choice rather than a universal scheme for older adults.
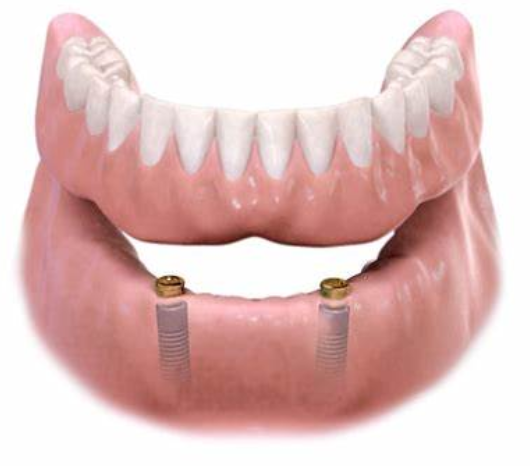
Implant overdentures: consider retention and the ability to manage it
When inadequate mandibular denture retention remains a major difficulty, an implant-retained overdenture may be an option after assessment of suitability and patient preference. Include attachment maintenance, removal and reinsertion, hygiene, and access to follow-up in the discussion.
In Müller et al. (2013), 16 dependent older adults received two-implant mandibular overdentures and 18 received conventional relines; mean ages were approximately 85 and 84 years. Overdentures improved stability and satisfaction, but chewing efficiency did not differ between groups and nutritional measures did not confirm a benefit. The small trial supports discussing retention-related benefit without promising nutritional improvement.
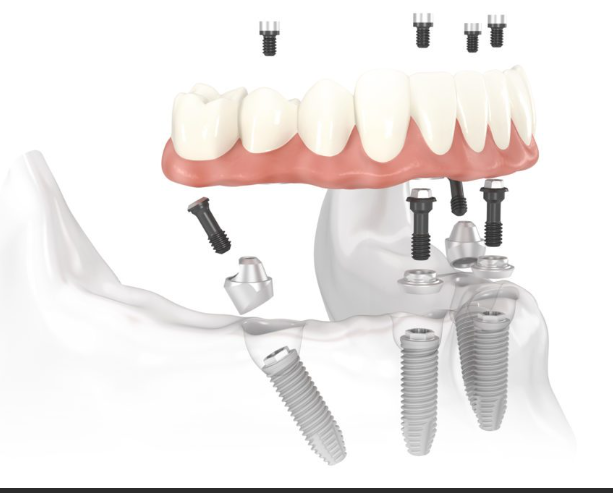
Fixed full-arch implant restorations: investigate the source of the problem
With discomfort, chipping, or loosening, examine the restoration, components, peri-implant tissues, hygiene access, and occlusal contacts together. The ACP maintenance statement includes biological and mechanical assessment at recall. A contact recording is only one part of investigating the problem.
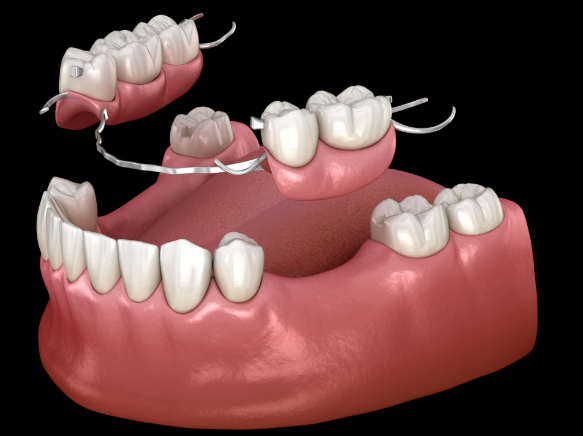
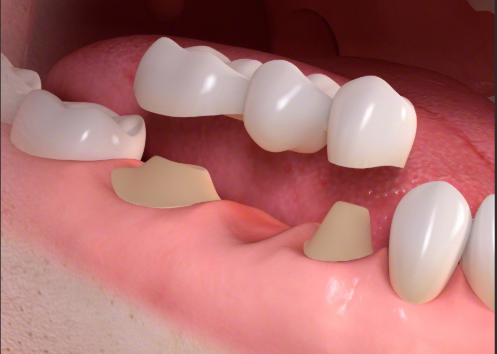
Partial dentures and tooth-supported restorations: use the remaining dentition
For a removable partial denture, relate the contacts to saddle support, framework fit, retention, and the condition of the remaining teeth. For a bridge or short-span restoration, document the abutments, opposing contacts, symptoms, and the change introduced by the restoration. Keep the intervention proportionate to the identified problem.
4. Use digital records to answer a defined question
Before recording, state what you need to learn and how the result could change the plan. Useful questions concern the sequence and distribution of contacts, or the movement to be represented in a digital design. Keep the recording alongside the examination and the patient’s symptoms.
| Record | Information supplied | Interpretation in practice |
|---|---|---|
| T-Scan | Relative occlusal force distribution and timing | Use the sequence and distribution to investigate a contact question. Relative readings are not absolute bite force in newtons. |
| OccluSense | Sensor-based occlusal pressure recording | Interpret the output using the manufacturer’s sensor and recording instructions; do not treat different systems’ scales as interchangeable. |
| Jaw-motion recording, such as MODJAW | Jaw motion integrated with three-dimensional models | Use the movement record to inform the relevant design question; confirm the result clinically. |

Manufacturer documentation describes what a system records. It does not establish that using it improves chewing, reduces complications, or selects the best geriatric occlusal scheme. A digital trace alone is not a sufficient reason for an irreversible adjustment.
5. Plan the review around the original complaint
Record what was changed and reassess the same problem: comfort during meals, prosthesis movement, foods avoided, tissue findings, and the ability to insert, remove, and clean the prosthesis. Compare with the baseline rather than judging success only by a more even-looking display.
Agree on review arrangements that match the intervention and the patient’s support needs. If the complaint persists, reconsider the diagnosis, prosthesis fit and support, salivary symptoms, and handling difficulties before repeating occlusal changes. Dietary or swallowing difficulties that remain outside the prosthodontic problem need appropriate assessment.
Clinical takeaway: Choose occlusal care from the cause of functional difficulty, the available support, and the patient’s goals. Use a proportionate intervention, add digital records when they answer a specific question, and judge the result by comfortable, usable everyday function.
References
References (10)
- Schimmel M et al. A conceptual model of oro-facial health with an emphasis on function. Journal of Oral Rehabilitation. 2021;48:1283–1294.
- Fortuna G et al. Impact of medications on salivary flow rate in patients with xerostomia. Clinical Oral Investigations. 2023;27:235–248.
- American College of Prosthodontists. The Frequency of Denture Replacement. Position statement.
- Kawai Y et al. A double blind randomized clinical trial comparing lingualized and fully bilateral balanced posterior occlusion for conventional complete dentures. Journal of Prosthodontic Research. 2017;61:113–122.
- Grech C et al. Patient Reported Outcomes on Different Occlusal Schemes in Complete Denture Wearers. International Journal of Prosthodontics. 2022;35:53–61. Published online 2021.
- Müller F et al. Implant-supported mandibular overdentures in very old adults: a randomized controlled trial. Journal of Dental Research. 2013;92(12 Suppl):154S–160S.
- American College of Prosthodontists. Maintenance of Full-Arch Implant Restorations. Position statement.
- Tekscan. IOS Scanner Occlusogram Occlusal Force Estimates Compared to T-Scan 10 Relative Occlusal Force Measurements. Manufacturer technical description.
- Dr. Jean Bausch GmbH & Co. KG. OccluSense sensor. Manufacturer documentation.
- MODJAW. Why 4D dentistry? Manufacturer workflow description.
Written by Dr Haitham Sharshar


Dr. Haitham Sharshar is an international digital dentistry speaker, educator, and digital occlusion consultant based in Cairo, Egypt. His work focuses on functional digital dentistry, CAD/CAM, implantology, jaw-motion analysis, and the integration of digital diagnostics into clinical treatment planning.
As Founder and Scientific Coordinator of Digital Dentistry Schoology (DDS), he has trained more than 3,270 dentists and dental technicians through university programs, international conferences, and hands-on courses. His teaching connects patient-specific diagnostic records with digital design and clinical workflows, helping clinicians and technicians understand how function and occlusion inform restorative planning.
Dr. Sharshar is a certified trainer for zebris JMA-Optic+ jaw-motion analysis and MyoWise dental EMG. His educational and consulting work brings together patient diagnostics, jaw-motion records, muscle-activity data, digital occlusion, and AI-supported workflows.
He is Founder and Clinical Director of Occlusa, an AI-supported platform for organizing clinical information and supporting clinician-led review and treatment planning. He also owns HS Dental Clinic in Cairo, where his clinical focus includes full-mouth digital rehabilitation and smile design.
His speaking and training topics include functional digital dentistry, digital occlusion, jaw-motion analysis, CAD/CAM workflows, digital implantology, and the practical integration of AI-supported tools into dental education and clinical practice.

WHERE DIGITAL MEETS CLINICAL