
Managing Tooth Proportions for Harmonious Smiles: A Comprehensive Guide to Aesthetic and Cosmetic Prosthodontics
When a patient says that their front teeth look too short, too wide or uneven, which measurement should guide the next step? Tooth proportions help describe the concern, but a numerical target cannot establish the diagnosis or predict satisfaction. A useful plan connects the patient’s preferences with tooth structure, gingival health, tooth position, lip display and function.
This guide explains how to use proportional analysis as a discussion and design aid, while separating measurements, preference studies and treatment decisions.
What does a tooth ratio actually measure?
Start by naming both dimensions and the view. A width-to-height percentage compares the width and height of the same tooth: width divided by height, multiplied by 100. An apparent inter-tooth width ratio compares two different teeth as seen from the front. Those measurements answer different questions and are not interchangeable.
- Anatomic crown dimensions: research on extracted teeth measures the crown itself. Magne, Gallucci and Belser’s 2003 study examined 146 extracted maxillary teeth, including worn and unworn groups. These data describe a selected specimen sample, rather than a prescribed smile.
- Visible clinical height: document where the gingival margin and incisal edge are located. A short visible crown may involve tissue coverage, wear, tooth position or a combination; the ratio does not identify the cause.
- Apparent frontal width: document the photograph and tooth orientation. A rotated tooth or an oblique view can change the visible width without changing its anatomic dimensions. Use consistent records and confirm dimensions clinically before transferring a photographic design.
As a calculation example, a width of 8.8 mm and a height of 11.0 mm give an 80% ratio. The same percentage can describe teeth of different absolute sizes. Record both dimensions, the measurement method and the reference points rather than transmitting a percentage alone.

Do golden, RED or Preston proportions define the ideal smile?
Golden proportion and RED: constructions, not diagnoses
In the dental golden-proportion construction, the apparent lateral-incisor width is about 62% of the central-incisor width, and the apparent canine width is about 62% of the lateral-incisor width. These are successive frontal-width comparisons, not width-to-height percentages. Shetty and colleagues describe these frameworks and found that a constant recurring proportion was not present in their 90-person natural-dentition sample. That sample does not establish a universal alternative.
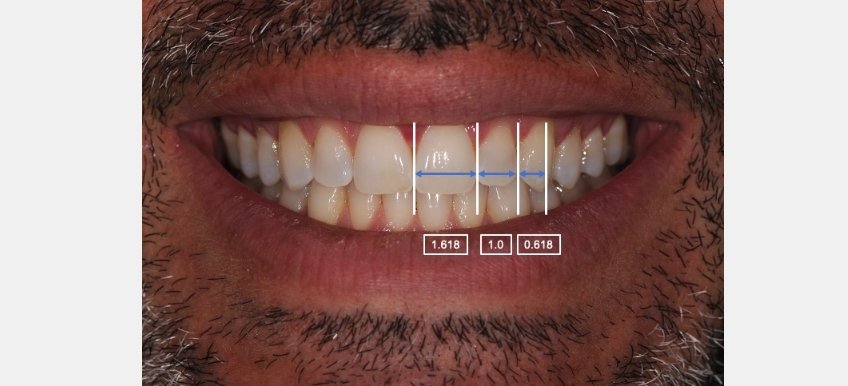
The recurring esthetic dental (RED) concept uses a selected constant ratio between successive apparent widths rather than requiring the golden value. Ward’s technique article describes a planning approach that also considers tooth length and the face. It is a design framework, not a diagnostic test or evidence that one formula improves long-term outcomes.
In Ward’s 2007 image-preference survey, 301 North American dentists compared constructed smiles. Preferences depended on the configurations shown; results for normal-length and tall teeth were not identical. This was a survey of dentists’ image preferences, not a prospective trial demonstrating better patient satisfaction, chewing function or restoration survival after RED-based treatment.
Preston’s proportions: keep the denominator clear
The Preston framework summarized by Shetty and colleagues uses an apparent lateral-incisor width of approximately 66% of the central incisor, and a canine width of approximately 55% of the central incisor. The canine-to-lateral relationship is therefore about 83.3% when calculated from these rounded values (55 divided by 66). It is not 83.3% of the central incisor. These values illustrate a historical proportional model, not compulsory dimensions for a patient.
Why a width-to-height range is not a treatment threshold
A commonly quoted range such as 75–85% should not be treated as an ideal that every central incisor must satisfy. In Cooper and colleagues’ cross-sectional perception study, one female smile was digitally modified and ranked by dentists, technicians and patients. An 82% ratio was most attractive for the normal-form central incisors in that stimulus set, but responses varied between and within groups. A preferred image does not establish that treatment to reach that number benefits an individual.
Wear also matters. Magne and colleagues reported different average anatomic ratios for worn and unworn teeth. A higher width-to-height ratio can arise when height is lost; it does not by itself show how much structure to add, whether to alter gingiva, or whether the bite should be changed.
Population studies should be interpreted just as carefully. Tsukiyama and colleagues’ 2012 extracted-tooth comparison reported more slender anterior teeth in its Asian sample than in its white sample. This does not support assigning an “Asian” or “white” target to a patient. Sample definitions, tooth type, wear and measurement method matter, and a group average cannot substitute for the person’s records and preferences.
How should proportional analysis change the plan?
The following is an educational decision sequence, not a patient-specific prescription. Use the measurements to clarify the problem and test options before committing to irreversible treatment.
- Identify the concern. Ask what the patient wants to change and what they want to preserve. Record the smile at rest and during movement, along with dental and periodontal findings. Do not assume the clinician’s preferred ratio is the patient’s preference.
- Identify the cause. Investigate wear, tissue coverage, tooth position, spacing and existing restorations. In worn dentitions, European consensus guidance emphasizes diagnosis, prevention, counseling and monitoring, with management based on severity, effects and patient wishes.
- Compare feasible options. Depending on the diagnosis, these may include observation, preventive care, orthodontic assessment, additive restoration or periodontal assessment. A numerical discrepancy alone does not justify veneers, crown lengthening or an increase in occlusal vertical dimension.
- Evaluate a proposed change. A diagnostic design or mock-up can support discussion of tooth length, shape, lip relationships and function. If increased vertical dimension is being considered, the 2025 SSRD/SEPES/PROSEC consensus emphasizes individualized planning and minimally invasive approaches. It also reports uncertainty about whether an evaluation phase is necessary in every case.
- Agree the limits and review. Discuss maintenance, alternative options and uncertainties. Before definitive treatment, assess the proposed contacts, occlusion, speech, tissue relationships and the patient’s response. Reassess comfort, appearance, function and tissue health after treatment rather than using the achieved percentage as the sole outcome.
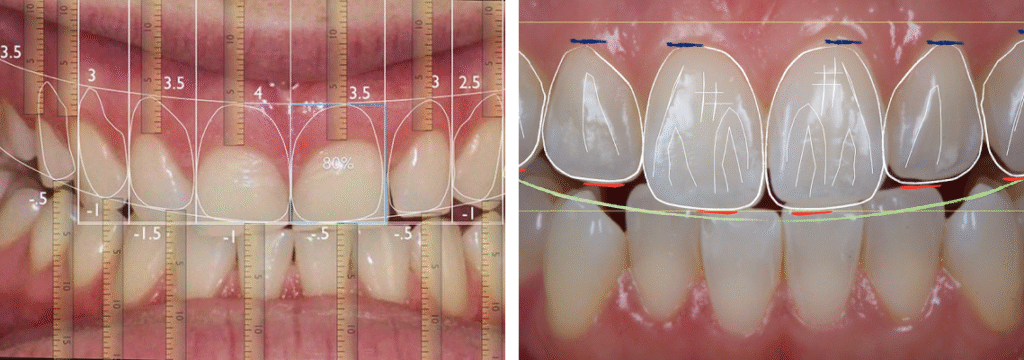
Two planning questions, without invented case outcomes
If central incisors appear short: first determine whether the apparent height reflects wear, gingival coverage or tooth position. Worn teeth do not automatically prove a loss of vertical dimension. A crown-lengthening or restorative plan needs its own diagnosis, assessment of tissues and function, and discussion of risk; a ratio alone cannot select it. The conservative approach in tooth-wear guidance is to establish the cause and control progression before considering restoration.
If anterior spaces are present: compare the proposed absolute tooth widths, tooth positions and distribution of space. Making every gap disappear by widening teeth may create a different aesthetic or functional problem. Discuss the available space-management options and preview the proposed result, without promising that a particular ratio will produce satisfaction. These are planning questions, not reports of actual patients or successful treatment.
What can software and measurement tools contribute?
Digital records can help the patient, clinician and laboratory compare a proposal, but the display must be interpreted in context. Digital Smile Design’s planning service describes simulations and mock-up files, and Smile Designer Pro describes digital design and simulation functions. These manufacturer descriptions establish available functions, not comparative accuracy, clinical superiority or a guaranteed postoperative appearance. Check the current version, file requirements and intended workflow before relying on a specific feature.
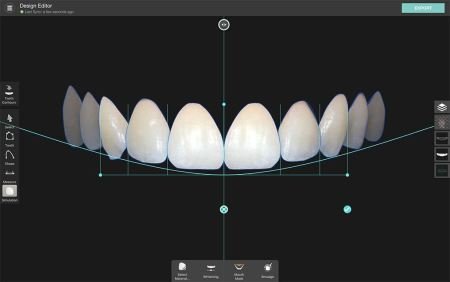
Choose a tool for the information needed. A photographic overlay can communicate shape; a calibrated measurement addresses dimensions; a clinical assessment determines whether the proposed change is appropriate. Do not treat a software template, an AI-generated smile or a face scan as validation of tissue health, occlusion or the patient’s preference.
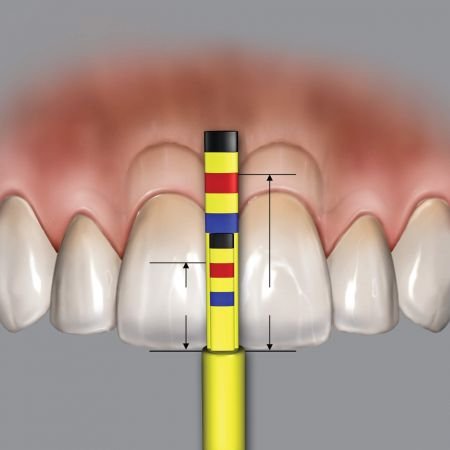
Chu’s Aesthetic Gauges are an example of a physical proportion tool. Reference marks can facilitate comparison, but they do not replace diagnosis. Similarly, a caliper’s displayed decimal places are not a universal accuracy specification. Check the specific instrument, its condition, calibration and the method of use. Prices and training needs also depend on the specific product and setting.

Practical takeaways for the dentist and laboratory
- For the dentist: use the patient’s concern and clinical diagnosis to select an appropriate plan. Perception research shows individual variation; discuss a proposal rather than imposing a fixed aesthetic formula.
- For the laboratory: request the actual width and height, measurement view, proposed incisal-edge position and relevant clinical records. Distinguish apparent frontal ratios from physical dimensions before designing a restoration.
- For both: record which decisions come from examination, which from a design proposal and which are supported by a study. Review the proposed appearance and function together. A well-documented proportion is useful communication, not proof of an ideal or successful smile.
References
Sources and evidence notes
- Magne P, Gallucci GO, Belser UC. Anatomic crown width/length ratios of unworn and worn maxillary teeth in white subjects. Journal of Prosthetic Dentistry. 2003;89:453–461. doi:10.1016/S0022-3913(03)00125-2.
- Cooper GE, Tredwin CJ, Cooper NT, Petrie A, Gill DS. The influence of maxillary central incisor height-to-width ratio on perceived smile aesthetics. British Dental Journal. 2012;212:589–599. doi:10.1038/sj.bdj.2012.522.
- Ward DH. A Study of Dentists’ Preferred Maxillary Anterior Tooth Width Proportions: Comparing the Recurring Esthetic Dental Proportion to Other Mathematical and Naturally Occurring Proportions. Journal of Esthetic and Restorative Dentistry. 2007;19:324–337; discussion 338–339. doi:10.1111/j.1708-8240.2007.00114.x.
- Shetty S, Pitti V, Satish Babu CL, Surendra Kumar GP, Jnanadev KR. To evaluate the validity of Recurring Esthetic Dental proportion in natural dentition. Journal of Conservative Dentistry. 2011;14:314–317. doi:10.4103/0972-0707.85824.
- Tsukiyama T, Marcushamer E, Griffin TJ, Arguello E, Magne P, Gallucci GO. Comparison of the anatomic crown width/length ratios of unworn and worn maxillary teeth in Asian and white subjects. Journal of Prosthetic Dentistry. 2012;107:11–16. doi:10.1016/S0022-3913(12)60009-2.
- Loomans B and colleagues. Severe Tooth Wear: European Consensus Statement on Management Guidelines. Journal of Adhesive Dentistry. 2017;19:111–119. doi:10.3290/j.jad.a38102.
- Ioannidis A and colleagues. Rehabilitation Strategies and Occlusal Vertical Dimension Considerations in the Management of Worn Dentitions: Consensus Statement From SSRD, SEPES, and PROSEC Conference on Minimally Invasive Restorations. Journal of Esthetic and Restorative Dentistry. 2025;37:702–706. doi:10.1111/jerd.13432.
- Ward DH. Proportional Smile Design: Using the Recurring Esthetic Dental Proportion to Correlate the Widths and Lengths of the Maxillary Anterior Teeth with the Size of the Face. Dental Clinics of North America. 2015;59:623–638. doi:10.1016/j.cden.2015.03.006.
- Digital Smile Design. DSD Interdisciplinary planning service. Manufacturer description of functions; not comparative outcome evidence.
- Smile Designer Pro. Software downloads and design/simulation description. Manufacturer information; not comparative outcome evidence.
- HuFriedyGroup. Chu’s Aesthetic Gauges Set. Manufacturer product identification; not a treatment indication.