
Integrating Evidence-Based Practice in Prosthodontics: Educational and Clinical Practice Insights
A new scanner, a faster appointment or an impressive survival percentage can prompt a useful clinical question. None, by itself, establishes that a treatment is better for the person in the chair. Evidence-based prosthodontics connects relevant research with clinical judgement and the patient’s priorities, then checks whether the chosen approach delivers the outcomes that matter.
This educational guide explains how to frame a prosthodontic question, appraise a study, teach the reasoning process and audit a change in practice. The examples below are identified studies with stated limits. They are not a systematic review or a patient-specific treatment protocol.
Start with the clinical question
The American Dental Association’s evidence-based dentistry framework combines scientific evidence, the dentist’s expertise, and the patient’s condition, needs and preferences. A conventional impression or an established restoration can fit that framework. Buying digital equipment does not establish that a practice is evidence-based.
Turn a broad question such as “Is digital dentistry better?” into one that can be answered. Specify the population, intervention, comparison and outcomes, often abbreviated PICO. For example: in adults needing a tooth-supported single crown, how does an intraoral scan compare with an elastomeric impression for patient discomfort, appointment time, restoration fit and later complications? The JADA guide to searching for clinical evidence explains how the question determines the evidence to seek.
A useful search record states the question, databases or guideline collections searched, search date and reasons for including a source. Look for a relevant current guideline or rigorous evidence synthesis, then inspect the primary studies when a treatment decision depends on their exact population or methods. Check for corrections or retractions and open the cited paper rather than relying on a plausible-looking title or DOI.
Check the evidence before applying it
Ask whether the study is trustworthy, whether its result matters and whether it applies to the proposed treatment. A randomized label is not a guarantee of low bias, and a pooled estimate is only as useful as the studies and methods behind it. Kiriakou and colleagues’ guide to interpreting trials and reviews discusses these appraisal principles.
- Population and setting: distinguish patients from typodont models, and single crowns from full-arch prostheses. Check the inclusion criteria and who was excluded.
- Comparison: identify the actual material, device, software version, operator experience and treatment steps. A historical comparison may reflect changes other than the intervention.
- Bias and missing data: examine allocation, assessor masking where feasible, participant losses, selective reporting and relevant funding or conflicts.
- Outcome and uncertainty: separate accuracy, comfort, time, survival, complications and satisfaction. Read effect sizes and confidence intervals, not only a p-value. Absence of a statistically significant difference does not establish equivalence.
- Applicability: decide what the evidence can support for this patient, and state what remains uncertain.
In a journal club, make the final step explicit: “This study informs this decision because …; it does not answer …”. That short statement often reveals when evidence from a laboratory test is being stretched into a promise about years of clinical service.
Clinical examples and their boundaries
Impression choice: patient experience is a distinct outcome
Gjelvold and colleagues’ randomized clinical trial included 42 patients needing tooth-supported single crowns or fixed partial prostheses of up to six units. In the tested workflow, digital impressions took less time and produced lower patient discomfort ratings than the conventional method. These findings support considering efficiency and patient experience for comparable care.
The trial does not establish that every scanner is more accurate, that the same advantage applies to an edentulous full arch, or that the resulting restorations have better long-term survival. Before changing the impression method, compare the study’s task and workflow with the planned restoration, and evaluate the clinical record produced.

Implant loading: match the restoration and site
A separate five-year randomized trial by Gjelvold, Kisch and Chrcanovic enrolled 50 patients with a missing maxillary tooth and compared immediate with delayed loading of single implants in healed sites. Its protocol excluded patients needing grafting or ridge augmentation at the implant site. The investigators reported similar clinical and aesthetic results within that setting.
That is not a full-arch rehabilitation study and does not justify transferring its results to fresh extraction sockets, grafted sites or different prosthesis designs. Read survival, success, tissue findings and prosthetic complications separately. A functioning implant can coexist with a maintenance need or an unsatisfactory aesthetic result. The paper illustrates why a treatment label such as “immediate loading” needs a precise clinical context.
Restorative materials: separate fit from longevity
For a CAD/CAM restoration, write down the exact question before comparing studies: is it about milling accuracy, fracture under a laboratory load, clinical survival or the need for repair? These outcomes should not be substituted for each other. A practical appraisal should record restoration type, material, supporting tooth or implant, follow-up duration, losses to follow-up and the definition of failure. Do not turn a material category or a digital manufacturing label into a universal longevity estimate.
Teaching evidence-based reasoning
Evidence-based teaching can assess both the technical task and the student’s explanation for choosing it. Veeraiyan and Sekhar’s randomized educational study assigned 42 undergraduate volunteers to conventional teaching alone or the same teaching plus critical appraisal exercises. The appraisal group had higher assessed preclinical tooth-preparation scores and greater self-confidence. This is relevant educational evidence, but it comes from one college and preclinical tasks. It does not establish better outcomes in treated patients.
Technology-learning outcomes need the same discipline. In Alfallaj and colleagues’ crossover experiment, 96 dental students compared digital scanning with conventional impressions on typodont models. Scanning was faster and was generally preferred. The study measured procedure time and perceptions, not long-term clinical competence, restoration survival or superiority of an entire residency curriculum.
A suggested teaching exercise: give learners a focused prosthodontic question and an identifiable primary study. Ask them to describe the study population, identify one important limitation and explain how a patient’s preferences could alter the decision. Assess that reasoning separately from the practical preparation or impression score. Use the same rubric across assessors and discuss disagreements. This is a proposed educational approach, not a reported institutional success story.
Evaluating a digital workflow
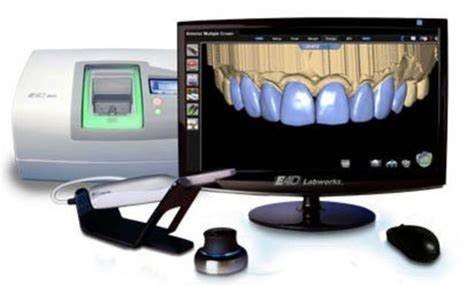
Use a digital tool when its particular contribution has been justified. The following is a practical purchasing and implementation checklist; it does not rank brands or claim that owning a system improves treatment outcomes.
- Scanning: identify the intended restoration and the surfaces that must be recorded. Require an acceptance check for the scan and bite record, and a plan when the record is inadequate.
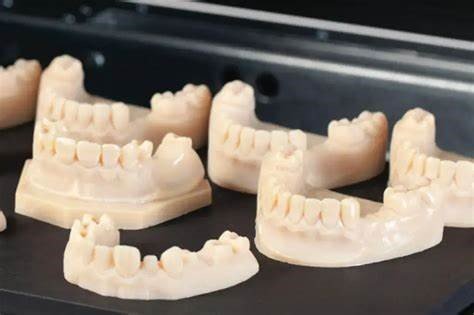
- Design and manufacturing: check compatibility across the design file, manufacturing system, exact material and intended use. Ask for the applicable manufacturer instructions rather than assuming that a printer validated for models is also validated for patient-worn restorations.
- Laboratory handoff: agree on file formats, version control, responsibility for design review and how remakes or missing information will be handled.
- Occlusal measurements: ask what a system actually measures, how repeatable it is and whether evidence shows that acting on the measurement benefits the relevant patient group. A colored contact display alone does not justify irreversible adjustment.
- AI or automated suggestions: ask for validation in the intended population, error-handling arrangements and clinician review. A confident-looking prediction is not evidence of improved patient care.

Keep the decision proportional to the evidence. A useful implementation record includes training needs, technical support, data handling, ongoing costs and a fallback workflow. Manufacturer information can establish the described product features or instructions; it should not be presented as independent proof of comparative clinical benefit.
Putting a change into practice
The patient discussion should explain the available options, meaningful benefits and harms, uncertainty, maintenance and likely burden of treatment. Record what the patient values, such as comfort, appearance, affordability or fewer visits, without treating one preference as universal. Reconcile those priorities with clinical suitability rather than assuming that a digital option is automatically preferred.
A suggested local audit: choose one bounded change, such as a new impression workflow for a defined restoration. Record a baseline using a consistent case definition, then review the same measures after training. Useful measures may include appointment duration, record rejection, remakes, adjustments, complications and a consistently collected patient-reported outcome. Specify the denominator and observation period, and retain unsuccessful cases and missed follow-up in the accounting.
A before-and-after improvement is a signal to investigate. Changes in case mix, operator experience or laboratory service may also explain it. Avoid describing a local audit as randomized evidence or using a percentage without its underlying counts. Set a review point, identify who owns the protocol and decide in advance what finding would prompt revision, more training or a return to the previous workflow.
Practical takeaways
- Start with a patient-relevant question, then choose sources capable of answering it.
- Check that the cited paper matches the claim, population, comparison and outcome.
- Keep technical performance, learning measures and patient outcomes distinct.
- Use individual studies as bounded examples within the wider evidence, not as universal treatment rules.
- Document the decision with the patient and review actual outcomes, including complications and uncertainty.
Evidence-based prosthodontics is an ongoing reasoning process. Digital methods can be evaluated within it, alongside conventional methods. The aim is a defensible, patient-centered decision with transparent limits and a way to learn from what happens next.
References
- American Dental Association. Clinical practice guidelines and dental evidence. Professional framework and guideline directory.
- Brignardello-Petersen R, Carrasco-Labra A, Booth HA, et al. Searching for evidence to inform clinical decisions. J Am Dent Assoc. 2014;145:1262–1267. doi:10.14219/jada.2014.113. Methods guidance.
- Kiriakou J, Pandis N, Madianos P, Polychronopoulou A. Interpreting randomized trials and systematic reviews. Prog Orthod. 2014;15:58. doi:10.1186/s40510-014-0058-5. Methods guidance.
- Gjelvold B, Chrcanovic BR, Korduner EK, Collin-Bagewitz I, Kisch J. Randomized clinical comparison of digital and conventional impressions. J Prosthodont. 2016;25:282–287. doi:10.1111/jopr.12410.
- Gjelvold B, Kisch J, Chrcanovic BR. Immediate versus delayed loading of single-tooth implants: five-year trial. J Clin Med. 2021;10:1077. doi:10.3390/jcm10051077.
- Veeraiyan DN, Sekhar P. Critical appraisal-based learning in an Indian dental college. J Dent Educ. 2013;77:1079–1085. Randomized educational study.
- Alfallaj HA, Alsaloum MA, Altuwaijri SH, Aldibasi OS, Alkadi LT. Digital scans and conventional impressions: student crossover experiment. Int J Dent. 2022;2022:6320251. doi:10.1155/2022/6320251.