
Digital Implant Planning: Accuracy and the Limits of Guided Surgery
How closely will the implant you place match the restoration-led plan on your screen? Digital planning and surgical guidance can help transfer that plan, but the achieved position still differs from the intended position. The useful clinical question is which records, checks and guidance method suit the site, rather than whether a system promises error-free surgery.
This DDS guide connects prosthetically driven planning with clinical accuracy evidence. It separates the proposed restoration, the planned implant and the implant actually placed, so that a useful digital preview does not become a promise about healing or long-term success.
What should the prosthetic plan determine?
A digital wax-up is a proposed restoration. It lets the restorative dentist, surgeon and technician discuss tooth position, restorative space, emergence, access for the prosthetic components and the intended occlusal relationship before choosing an implant position. The plan must then be reconciled with the available bone and nearby anatomical structures. A pleasing tooth arrangement alone does not establish a suitable surgical site.
Manufacturer workflows illustrate this connection: DTX Studio Implant combines tomographic data with optional dental scans and a diagnostic tooth setup to support treatment planning and surgical-template design. These are planning functions, not evidence that a wax-up prevents recession, prosthetic complications or implant failure.
What do CBCT and surface scans actually contribute?
CBCT supplies three-dimensional radiographic information for evaluating bone dimensions and relevant anatomical boundaries. An intraoral or laboratory surface scan supplies surface geometry; the proposed restoration adds the restorative objective. Their alignment must be checked in the planning software. Review the source images and the registered surfaces rather than relying only on an attractive three-dimensional rendering. The DTX Studio Implant 3.6 instructions describe the product-specific checks and limitations; other systems require their own compatible instructions.
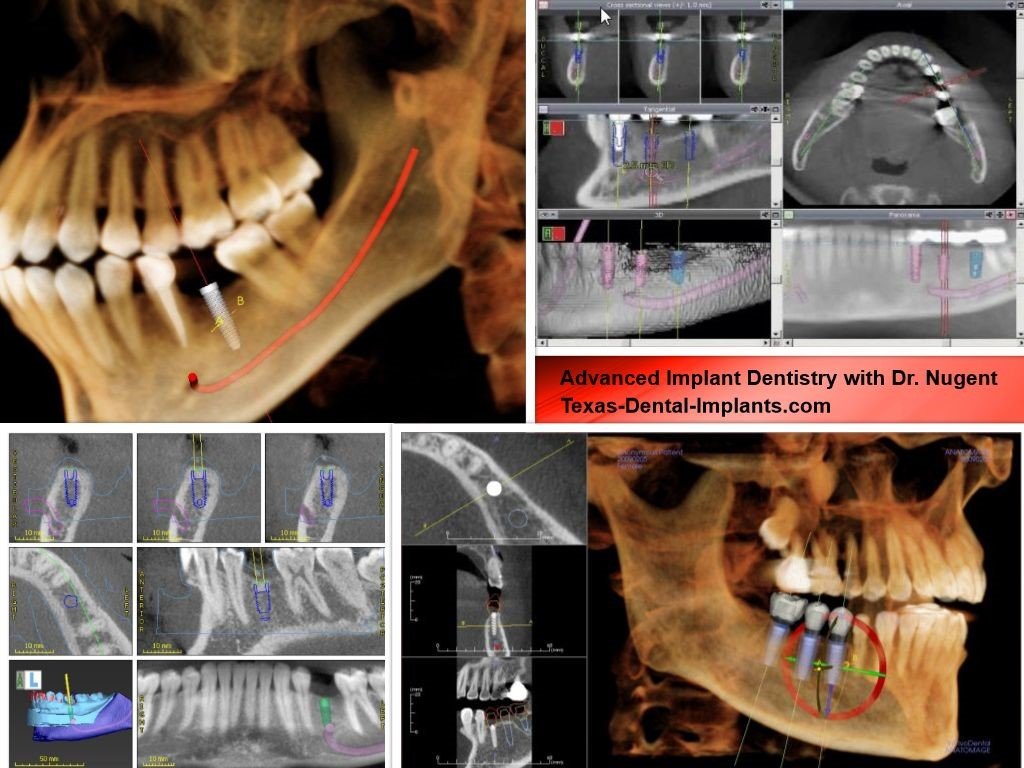
Bone dimensions and bone density are different questions. In a phantom investigation involving 13 CBCT devices and one multislice CT device, Pauwels and colleagues found that good overall correlation could coexist with substantial errors in quantitative grey values. Do not treat an arbitrary CBCT grey value as a calibrated Hounsfield unit or use it alone to decide on grafting or primary stability. That laboratory study does not establish the performance of every current scanner or validated calibration method.
Surface scanning also needs a context-specific accuracy assessment. Avoid describing it as distortion-free or claiming that every scanner integrates seamlessly with every planning system. For the chosen scanner, software and implant components, check supported file formats, the acquired area and the quality of the alignment before committing to the plan.
What does “accurate implant placement” mean?
Clinical accuracy studies commonly compare the planned and achieved implant positions at the platform, apex and long axis. Linear deviations in millimetres and angular deviations in degrees answer different questions. A mean is a group summary, not a maximum error or a safety allowance for an individual site.
In Block and colleagues’ prospective cohort, 478 patients received 714 implants across fully guided dynamic navigation, partially guided navigation and freehand approaches. For the fully guided navigation group, mean global platform deviation was 1.16 ± 0.59 mm, mean global apical deviation 1.29 ± 0.65 mm and angular deviation 2.97 ± 2.09° (means ± standard deviations). Navigation groups had smaller deviations than freehand in that study. The figures demonstrate residual clinical error; they do not support a blanket submillimetre guarantee or describe every navigation system.
Accuracy is also distinct from the patient’s experience. In Jorba-García and colleagues’ randomized clinical trial in partially edentulous patients, dynamic navigation reduced angular and most linear deviations compared with freehand; apical vertical deviation did not differ significantly. Navigation took about 14 minutes longer. Postoperative pain and analgesic use were similar, and satisfaction did not appear better. These short-term findings neither establish improved long-term implant survival nor rule out benefits in other settings.
Should you use a static guide or dynamic navigation?
Static guidance transfers the plan through a manufactured template. The supported drilling and implant-insertion steps depend on the guide and instrument system. Check the intended support, seating, access and component compatibility under the relevant instructions. A fixed guide cannot simply change its designed trajectory; an unexpected finding requires a clinical reassessment and an appropriate alternative plan. It does not make intraoperative decision-making impossible.
Dynamic navigation displays tracked instrument position relative to the registered plan. Examples include X-Guide and Navident. The display depends on registration, calibration and tracking; it is not a real-time measurement of bone density. X-Nav’s X-Clip calibration guide, for example, calls for calibration before each surgery and for each X-Clip, with recalibration if an instrument must be resecured. That document is specific to the stated setup and does not replace training or the applicable full instructions.
Direct comparisons do not justify ranking one approach as universally more accurate. In Kaewsiri and colleagues’ randomized trial, one surgeon placed single implants in 60 patients, with 30 allocated to each method. Mean platform and apical deviations were 0.97 and 1.28 mm with static guidance, and 1.05 and 1.29 mm with dynamic navigation. The principal platform, apex and angular differences were not statistically significant; a directional analysis found greater mesial deviation with dynamic navigation. This does not prove equivalence across operators, systems or indications.
As a practical interpretation of these findings, assess access, reliable guide support or tracking, the team’s training and the complete planning-to-surgery process. Do not assign a universal cost advantage, minimal learning curve or shorter operating time to either method. A clinical accuracy result from one study is not a price comparison or a measure of proficiency.
What can planning software and AI reasonably promise?
Simplant and BlueSkyPlan describe implant-planning and guide-related workflows. Supported implants, components and exports must be checked for the actual version and configuration. Product availability or a three-dimensional implant preview does not demonstrate bite-force simulation, autonomous clinical decisions or fewer implant failures.
AI features need the same discipline. Nobel Biocare describes DTX Studio Clinic’s assisted implant planning as proposing implants and virtual crowns for clinician adjustment. A proposed position still requires assessment against the patient’s anatomy, restorative needs and source records. Automated alignment, segmentation or tooth setup should not be relabelled as a validated prediction of healing, comfort or long-term success. Manufacturer feature descriptions support the stated functions, not comparative clinical superiority.
What should the team take into the next case?
The clinical evidence supports using guidance to assist transfer of a considered plan while retaining room for residual error and clinical judgment. The following are educational interpretations of the evidence and product limitations above:
- For the restorative dentist and surgeon: agree the intended restoration, then reconcile the implant position with the anatomical records. Review an alignment that looks inconsistent before relying on the plan.
- For the surgeon: distinguish study averages from case-specific safety planning. Follow the applicable system’s checks and reassess if seating, tracking or intraoperative findings are inconsistent with the plan.
- For the technician: keep the approved restoration proposal and implant plan identifiable, and confirm the selected components and manufacturing route. A virtual wax-up remains a proposal until the clinical and laboratory stages have been assessed.
- For the patient discussion: explain what guidance assists and what remains uncertain. Improved positional accuracy does not itself promise less pain, faster treatment or longer implant survival.
References and product documentation
- Block MS, Emery RW, Cullum DR, Sheikh A. Implant Placement Is More Accurate Using Dynamic Navigation. Journal of Oral and Maxillofacial Surgery. 2017;75:1377–1386. Primary prospective cohort.
- Jorba-García A, et al. Accuracy of dental implant placement with or without the use of a dynamic navigation assisted system: A randomized clinical trial. Clinical Oral Implants Research. 2023;34:438–449. Primary randomized trial.
- Kaewsiri D, et al. The accuracy of static vs. dynamic computer-assisted implant surgery in single tooth space: A randomized controlled trial. Clinical Oral Implants Research. 2019;30:505–514. Primary randomized trial.
- Pauwels R, et al. Variability of dental cone beam CT grey values for density estimations. British Journal of Radiology. 2013;86:20120135. Primary phantom investigation.
- Nobel Biocare. DTX Studio Implant 3.6 instructions for use and DTX Studio Clinic feature description. Manufacturer documentation.
- X-Nav Technologies. X-Clip calibration quick reference, P010261 Rev. B. Manufacturer instructions for the named setup.