
Direct Composite Veneers: Advanced Techniques and Case Selection for Aesthetic Excellence
Direct composite veneers can change anterior tooth shape and appearance while allowing a conservative, repair-oriented approach. Their value depends on the tooth, the desired change and the patient’s willingness to maintain the restoration. Clinical studies report surface deterioration and reinterventions as well as restorations that remain in service. Neither a filler label nor a digital preview establishes a superior material or a guaranteed lifespan. [1] [2]
This DDS teaching guide connects the evidence to case selection, preparation, layering, finishing and follow-up. The practical checkpoints below are educational interpretations of the cited research and technical guidance, rather than a treatment prescription for an individual patient.
What does the clinical evidence actually show?
Gresnigt, Kalk and Özcan evaluated 96 direct laminate veneers in 23 patients in a randomized split-mouth trial. At a mean observation of 41.3 months, the two tested microhybrid systems did not show a statistically significant survival difference. Surface roughness and marginal discoloration were the main qualitative changes. This is evidence about those materials and that clinical protocol; it is not a five-year comparison of all nanofilled and microhybrid veneers. [1]
Mazzetti and colleagues’ practice-based study examined 1,459 direct composite and ceramic veneers in 341 patients. Ceramic veneers had better observed longevity, and composite veneers required more reinterventions. Because treatment was not randomly assigned, the findings should inform discussion of maintenance rather than be read as proof that one material is best for every patient. Importantly, the study distinguished restorations remaining in service after repair from restorations requiring no repair. [2]
Frese and colleagues followed 176 direct composite buildups used to reshape teeth or close spaces. Restorations with unfavorable events were repaired and remained in place. These additive buildups are relevant to conservative care, but they are not interchangeable with full facial veneers or evidence for a universal veneer survival percentage. [3]
When is a direct approach worth considering?
Begin with the patient’s concern and a clinical examination, not a material category. FDI identifies defect extent, tooth–material interaction, caries risk, behavior such as bruxism and operator factors as relevant to direct restoration performance. [4] Translate those considerations into a case-specific discussion:
- Define the concern: shape, spacing, color or an existing restoration.
- Examine remaining tissue, restorations, oral health, hygiene access and functional loading.
- Consider whether observation, orthodontic assessment, color treatment or another restoration could address the concern.
- Discuss maintenance, repair, replacement and costs before agreeing on treatment.
These are planning questions, not eligibility cutoffs. Severe discoloration, crowding or heavy loading should prompt further assessment; none establishes an automatic indication for composite or ceramic veneers.
How much preparation is justified?
An additive design is possible in selected recontouring and space-closure situations, as illustrated by the Frese study. It does not follow that every veneer can be placed without preparation. [3] The required restorative space, proposed contour and remaining enamel must be assessed together.
LeSage’s actual veneer-preparation publication is a 2013 classification proposal. It describes preparation in terms of space, remaining enamel and exposed dentin; it is not a direct-veneer trial demonstrating a particular bond-strength improvement. Use that framework to explain what would be removed and why, rather than applying a universal facial-reduction depth. [5]
A practical checkpoint is whether the planned restoration can achieve the agreed form without excessive bulk or unnecessary reduction. If it cannot, revisit the design or treatment option. Conservative preparation is not the same as reversibility: removal of sound tooth tissue is irreversible, and future restoration replacement can enlarge the intervention. [6]
Does every veneer need complex layering?
Layering gives the clinician ways to distribute opacity, translucency and characterization. Ardu and Krejci described a biomimetic layering technique for large anterior Class IV restorations. That technical paper helps explain the concept, but it does not supply five-year veneer color-change measurements or a comparative clinical polishing benefit. [7]
Elzayat and colleagues compared dual-shade and polychromatic layering in 42 participants with 84 Class III or IV anterior restorations. At one year, they found no statistically significant difference in patient satisfaction or color-match outcomes; surface luster was an exception among the assessed criteria. This was not a veneer-only trial, and absence of a statistically significant difference does not prove equivalence. It does not establish a percentage of successful veneer cases or a predictable saving in minutes. [8]
For practice, choose the simplest approach that can address the actual substrate and intended appearance, then assess the result. The shade names, opacities and curing requirements belong to the exact restorative system. Solventum’s Filtek Supreme Ultra technique guide, for example, gives separate shade- and light-dependent instructions and directs the clinician to the adhesive’s own instructions. Those settings should not be generalized to other brands. [9]
What can an index or digital plan contribute?
A wax-up and index can provide a proposed external form for discussion and transfer. GC’s G-ænial Universal Injectable technical manual illustrates injection molding and a separate stamp technique. These are technique descriptions, not comparative evidence that an index guarantees fewer voids, better margins or faster treatment. [10]
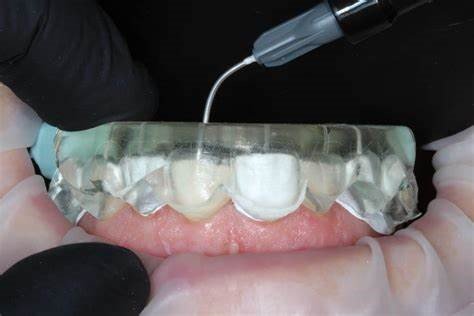
Before using an index, assess its seating, access for material placement, contact separation and the intended contours. After removal, examine the actual restoration rather than assuming the transferred form is acceptable. A printed model, a clear matrix and the composite restoration have different roles; the index does not replace clinical finishing or assessment.
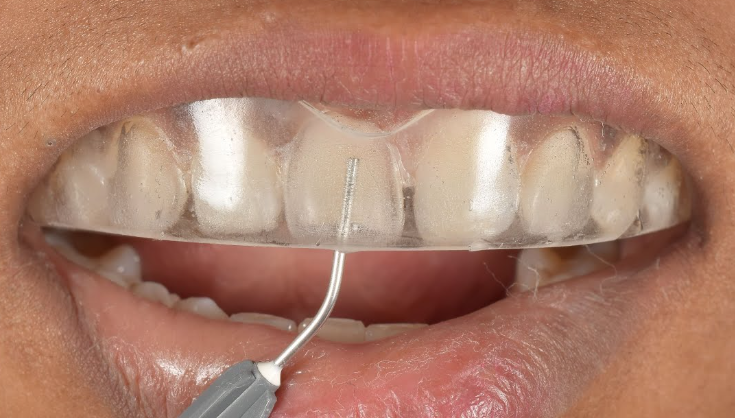
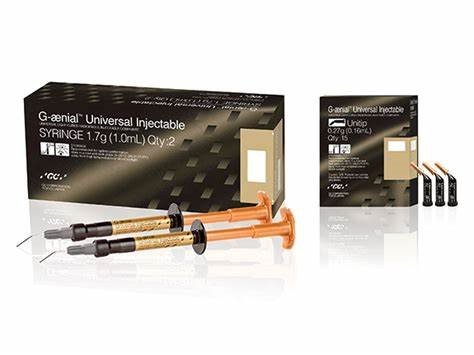
The existing product photograph below shows G-ænial Universal Injectable, not the entire G-ænial family. Its instructions address isolation, compatible bonding, incremental placement and shade-dependent curing. Follow the current regional instructions for the exact product and indication; an injectable consistency is not permission to use any flowable material for any veneer. [11]
How should finishing and polishing be planned?
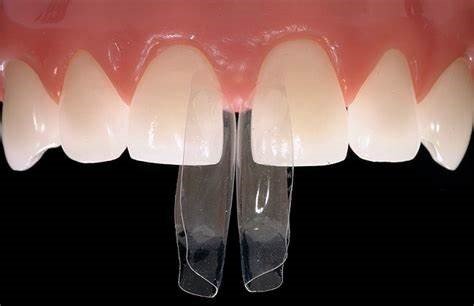
Finishing establishes contours and removes unwanted excess; polishing refines the surface. The specific instrument, abrasive sequence, pressure and speed should match the material and the manufacturer’s instructions. A smooth appearance immediately after treatment does not establish long-term color stability.
Jiffy Original Composite System is identified by Ultradent as a composite finishing and polishing system. The image shows the composite kit, which should not be confused with the brand’s ceramic system. [12]

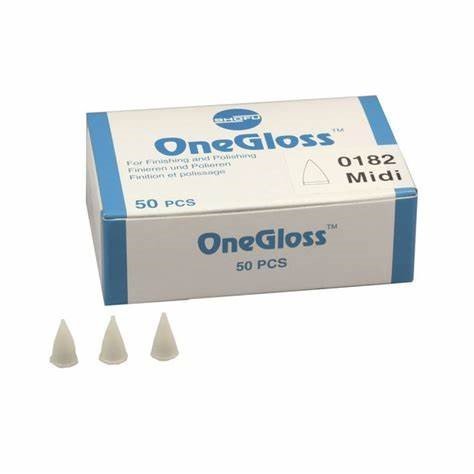
OneGloss is an aluminum-oxide finishing/polishing product family. Shofu distinguishes OneGloss and OneGloss PS and their mounting arrangements. Single-product finishing is different from a sequence combining separate abrasives. Check the current instructions for the exact point and mandrel rather than combining incompatible descriptions. [13]
What belongs in follow-up?
Review the patient’s symptoms and satisfaction alongside restoration form, contacts, surface texture, marginal condition and signs of disease. The surface changes reported in the direct-veneer trial justify discussing maintenance, but do not establish a universal polishing interval or a quantified reduction in color change. [1]
FDI distinguishes refurbishment, repair and replacement. Superficial staining or excess contour may be managed differently from a deeper defect, fracture or disease. Identify the cause and assess the restored tooth as a whole before intervening. Repair can conserve tissue when appropriate; it is not suitable for every failure and is not the same outcome as an untouched restoration. [6]
How do these decisions apply to common presentations?
- Space closure: ask whether an additive design can produce acceptable proportions and contacts, and whether the cause of the spacing requires another treatment first. The buildup cohort supports considering conservative additions, not a guaranteed result. [3]
- Marked discoloration: assess whether the proposed material and available space can deliver an acceptable appearance before committing to reduction. Do not promise complete masking from a generic composite category. [5]
- Wear or repeated chipping: investigate the functional and patient factors rather than assuming that a more elaborate layering technique will solve the problem. [4]
These are educational decision points, not case reports. Outcomes for an individual patient cannot be predicted from these examples.
Clinical takeaway
- Select the treatment before the material: assess the desired change, tooth tissue, disease and functional risks. The clinical evidence supports selective use with limitations, not a blanket superiority claim. [4]
- Use a product-specific technique: plan the contour and optical effect, preserve suitable tissue, isolate, bond and cure according to the actual system. An index assists transfer but cannot certify the finished restoration. [9] [11]
- Plan for maintenance: explain the difference between survival, repair and intervention-free success. Reassess defects and their cause before choosing refurbishment, repair or replacement. [2] [6]
References and product instructions
- Gresnigt MMM, Kalk W, Özcan M. Randomized controlled split-mouth clinical trial of direct laminate veneers with two micro-hybrid resin composites. Journal of Dentistry. 2012;40:766–775. Study record and abstract.
- Mazzetti T et al. 10-year practice-based evaluation of ceramic and direct composite veneers. Dental Materials. 2022;38:898–906. Study record and abstract.
- Frese C, Schiller P, Staehle HJ, Wolff D. Recontouring teeth and closing diastemas with direct composite buildups: a 5-year follow-up. Journal of Dentistry. 2013;41:979–985. Study record and abstract.
- FDI World Dental Federation. Alternative direct restorative materials to dental amalgam. Policy statement, 2023. General restorative risk factors; not a veneer comparison. FDI statement.
- LeSage B. Establishing a classification system and criteria for veneer preparations. Compendium of Continuing Education in Dentistry. 2013;34:104–115. Classification proposal, not a survival or bond-strength trial. Publication record.
- FDI World Dental Federation. Repair of Restorations. Policy statement, 2019. FDI statement.
- Ardu S, Krejci I. Biomimetic direct composite stratification technique for the restoration of anterior teeth. Quintessence International. 2006;37:167–174. Technical description of Class IV restorations. Publication record and abstract.
- Elzayat GA, Elsayed ME, El Zoghby A. Clinical Performance of Direct Anterior Composite Restorations Using Esthetic Dual-Shade versus Polychromatic Natural Layering Technique: a split mouth randomized controlled clinical trial. Brazilian Dental Science. 2020;23(4). Journal article.
- Solventum. Filtek Supreme Ultra Universal Restorative technique guide. Manufacturer guidance for the named system. Technique guide.
- GC. G-ænial Universal Injectable Technical Manual. Version 1.0, October 2018, injection molding and stamp sections. Manufacturer technique guidance. Technical manual.
- GC. G-ænial Universal Injectable instructions for use. Refer to the current regional version for the actual product and indication. Instructions for use.
- Ultradent. Jiffy Original Composite System, product information and instructions. Manufacturer resource.
- Shofu. OneGloss and OneGloss PS product chart. Manufacturer resource.