
Digital Transformation in Dentistry: Comparing Modern Oral Scanning Technologies
Which intraoral scanner fits the work your practice actually does? Start with the clinical indication and the complete workflow: what must be recorded, how the laboratory will use it, and how the final result will be checked. Digital impressions can support restorative, orthodontic and implant care, but a scanner’s advertised speed or accuracy does not establish the fit of every restoration or the outcome for every patient.
This guide compares established scanner families and explains how to interpret the evidence behind them. Manufacturer features describe the named configuration; clinical and laboratory studies answer narrower questions. Neither is a universal ranking of current systems.
What does scanner accuracy mean?
An intraoral scanner records visible surfaces and software combines successive views into a three-dimensional model. Optical acquisition, reconstruction and alignment all contribute to the final dataset. A dense, attractive mesh is useful for inspection, but its appearance alone does not establish measurement accuracy.
Trueness describes agreement with a reference; precision describes agreement between repeated measurements. Surface deviation, crown marginal gap, implant-position error and diagnostic sensitivity are different endpoints. They should not occupy the same accuracy column. A laboratory reference cast also presents different conditions from a moving patient.
For example, Ender, Zimmermann and Mehl’s 2019 laboratory comparison tested eight scanner hardware/software configurations and a conventional impression method, with ten repetitions per group. Complete-arch median trueness across the tested methods ranged from 16.3 to 89.8 micrometres. These were surface-deviation results calculated using the study’s percentile-based analysis, not crown-fit measurements. Partial-arch and complete-arch results differed; the authors called for clinical confirmation. The experiment cannot rank today’s TRIOS 5, i700 Wireless or iTero 5D Plus, which were not the tested configurations.
When reading a specification, ask which arch span, surface, reference method, software version and statistic it describes. Point-acquisition rate and camera frame rate describe data capture, not submicrometre clinical precision. A single number cannot summarize all indications.
Comparing scanner systems
The practical differences are often configuration, connection to the laboratory, ergonomics, diagnostic options and support. Confirm the exact device and local software package before purchase; a feature on one generation or configuration should not be assumed on another.
Dentsply Sirona Primescan

Dentsply Sirona describes the original Primescan’s acquisition as dynamic depth scanning with a Smart Pixel sensor. Its product brochure specifies a measuring depth up to 20 mm and processing of more than one million 3D points per second. These manufacturer specifications are not evidence that covered margins can be recorded or that a complete arch will have negligible distortion. Distinguish the original Primescan configuration from newer products, and check the selected software’s laboratory-transfer and chairside-manufacturing options.
Cleaning and sterilization depend on the sleeve. The manufacturer’s CEREC system documentation distinguishes reprocessing options and limits autoclaving to the applicable sleeve. Follow the current instructions for the exact accessory rather than treating every tip as autoclavable.
3Shape TRIOS 5
3Shape’s TRIOS 5 information emphasizes wireless scanning, ScanAssist alignment and connectivity. These functions support acquisition; they do not remove the need to inspect the recorded surfaces and bite relationship. Diagnostic functionality must be matched to the model and market: the US K242103 clearance identifies TRIOS 5 model L1P-1F as an aid in caries diagnosis. That specific indication does not establish identical capabilities for every TRIOS 5 unit or replace a clinical assessment. Confirm the hardware, enabled software and current local instructions.
Align Technology iTero Element 5D Plus
The iTero Element Plus series combines three-dimensional scanning with intraoral images and, in the applicable 5D Plus configuration, near-infrared imaging (NIRI). The Lite configuration excludes NIRI. Invisalign connectivity, visualization and longitudinal comparison can be relevant to orthodontic workflows, but a simulated smile is a proposed outcome, not a prediction of biological tooth movement.
The manufacturer’s 5D/5D Plus user manual describes NIRI as an adjunct to the existing standard of care for caries detection. Colour images and a prescription’s shade-selection field should not be assumed to constitute validated automated shade matching.
Medit i700 Wireless
The Medit i700 Wireless product page lists a 328 g handpiece, a remote-control button, reversible tip and up to 70 frames per second. The wired i700 is a different configuration, listed at 245 g. The distinction matters when assessing handling, batteries and workstation arrangements. Neither weight nor frame rate establishes impression accuracy. Confirm the current software, optional services, export route and support terms instead of assuming every future feature is subscription-free.
DEXIS IS 3800 family
For practices considering the scanner family previously associated with Carestream, check the precise model and support arrangements. The current DEXIS IS 3800 product documentation describes the wired model and IS ScanFlow workflows, with laboratory transfers including STL, PLY and OBJ. Wired IS 3800 and wireless IS 3800W are separate configurations. A vendor’s scan-time demonstration on a stone model should not be presented as total chair time for a patient.
From a preparation to a restoration
For a crown or short-span restoration, the key question is whether the preparation, finish line, adjacent surfaces and opposing relationship are usable for design. An optical system cannot recover a margin simply because the software draws a continuous-looking surface. Access, tissue position and an adequately controlled field still matter. The iTero 5D/5D Plus manual, for example, calls for a dry preparation, a tissue-free margin and control of debris, saliva and blood when scanning fixed restorative cases.
In Son and Lee’s 2021 model experiment, equigingival and subgingival finish lines were less accurately captured than more accessible margins, and displacement cord improved the recorded accuracy. The devices were Medit i500 and EZIS PO; these results explain the importance of access but do not supply a universal clinical threshold or a protocol for every patient.
Impression accuracy is only one contribution to final fit. In a clinical study of sixteen participants requiring single molar crowns, Sakornwimon and Leevailoj found no statistically significant difference in zirconia crown marginal discrepancy between digital and polyvinyl-siloxane impressions. Participants generally preferred digital impressions, although the occlusal-registration ratings did not differ significantly. This separates two useful outcomes: patient experience can improve without a demonstrated improvement in marginal fit.
A practical restorative sequence is to inspect the preparation and recorded margin before export, confirm the bite and laboratory prescription, and review the manufactured restoration for seating, contacts and occlusion. If a critical surface is absent or uncertain, correct the acquisition problem before design. Rescanning or a suitable conventional impression remains an option; an automatically completed mesh is not a substitute for a verified record.
Orthodontic records and patient communication
Digital models can be transferred into compatible orthodontic planning workflows and used to discuss tooth position and proposed treatment. Their value is clearest when the clinician explains what the model shows, what the proposed movement assumes and which additional records are needed. An attractive simulation should not be used as a guarantee of the final smile or a reason to omit diagnostic assessment.
Preference for a scanning procedure is not the same as acceptance of orthodontic treatment. In Yuzbasioglu and colleagues’ study of twenty-four participants, people preferred digital impressions and the tested scanning procedure took less time. Conventional impressions were taken first, followed by CEREC Omnicam scans two weeks later, so order effects and the particular devices limit interpretation. The study did not measure whether a visual simulation increased orthodontic treatment acceptance.
For a combined orthodontic-restorative plan, agree on the required records and final restorative space with the laboratory and treating clinicians. Compare later scans with their acquisition and alignment conditions in mind. Use the visualization to invite questions about options and limitations, rather than assigning a universal improvement in consent, adherence or satisfaction.
Implant impressions and surgical planning
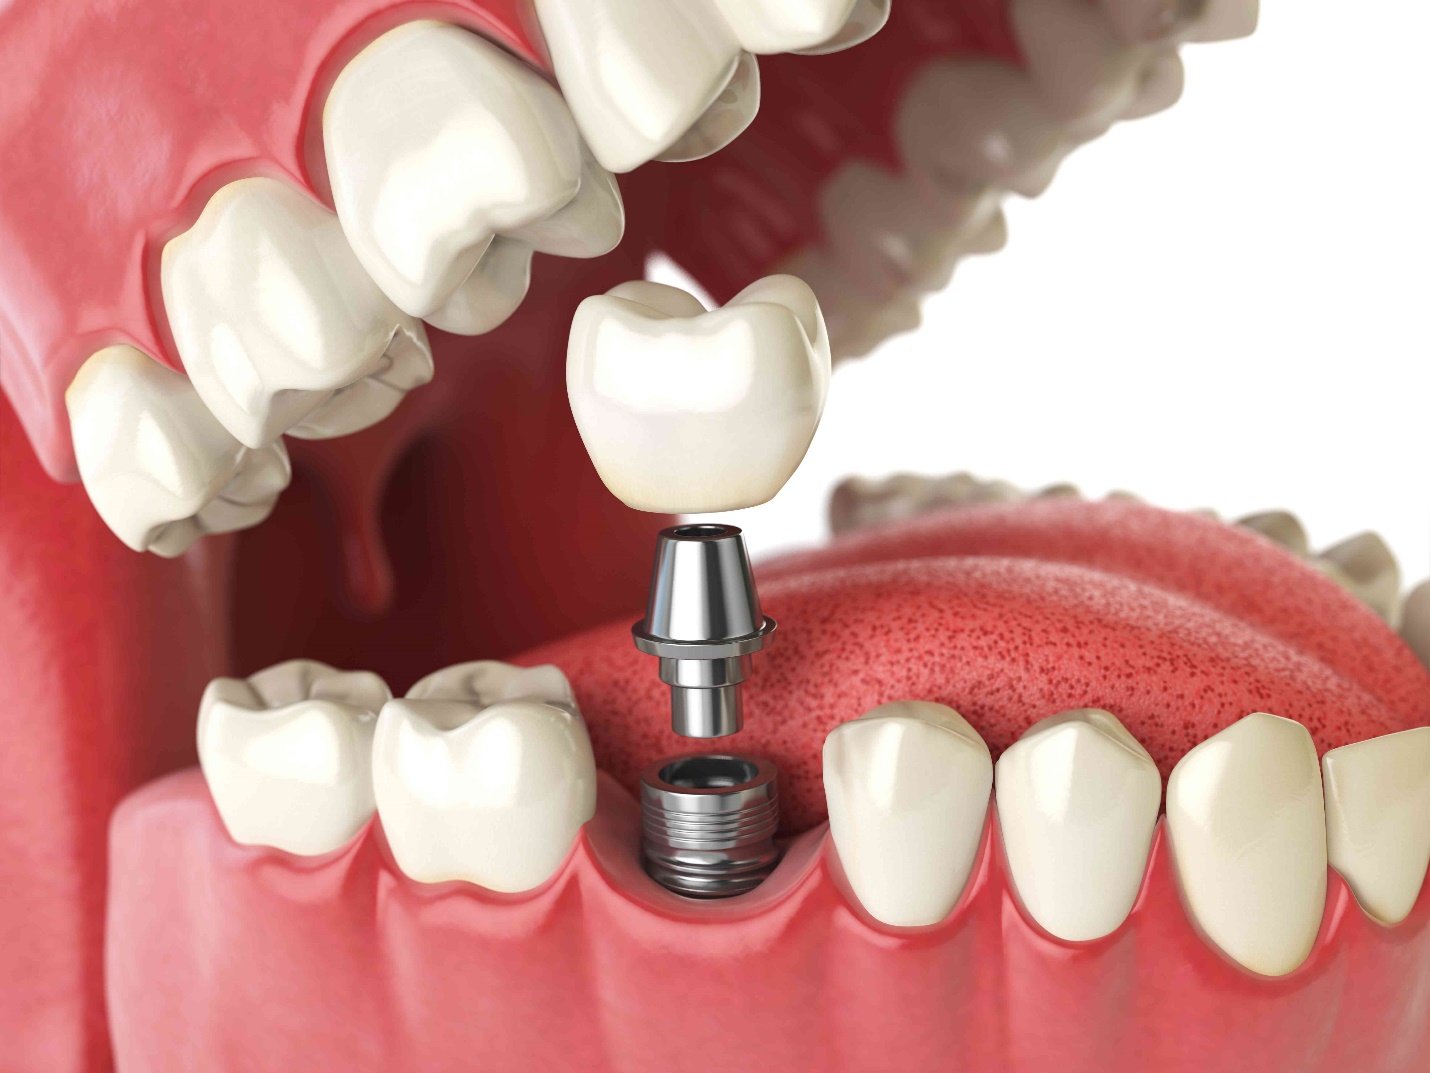
Keep two digital tasks separate. An implant impression records the position of an existing implant through compatible scan components and library data. Surgical planning combines anatomical and prosthetic information to plan an implant that has not yet been placed. An intraoral surface scan does not show the underlying bone, and its accuracy is not the same as the accuracy of guide placement or surgical navigation.
In Lee and colleagues’ crossover clinical trial involving thirty participants, digital scanning for single implant-supported restorations took less total impression time than the conventional workflow and produced comparable clinical accuracy. Digital rescanning took longer than conventional remakes in that study. These findings support a workflow option for the studied indication; they do not establish a fixed reduction in visits for a full-mouth rehabilitation.
Likewise, a randomized trial by Jorba-García and colleagues found that dynamic navigation reduced several placement deviations compared with freehand surgery, but increased surgical time and did not improve patient satisfaction or postoperative pain. Surgical accuracy, patient experience and impression efficiency should therefore be assessed separately. No navigation workflow removes the need for anatomical safety planning and intraoperative judgment.
Before a full-arch implant restoration, verify component compatibility, scan-body seating and capture, interimplant relationships and the planned prosthetic verification steps. Do not extend single-implant findings to an edentulous full arch without indication-specific evidence. A successful digital file transfer is an intermediate step, not proof of passive fit or a completed clinical result.
Choosing and integrating a scanner
Begin with representative cases from your practice and a laboratory partner who can test the proposed handover. A useful trial follows the record through acquisition, export, design and delivery instead of ending when a colourful model appears on screen. Consider the following questions:
- Indication: Is the evidence relevant to single teeth, short spans, orthodontic models, removable prostheses or full-arch implants?
- Interoperability: Can your laboratory open the actual exported file, retain the needed colour or prescription information and use the required component library? An STL export alone does not guarantee compatibility with every service.
- Clinical checks: Can the team recognize incomplete margins, an unreliable bite record and unsuitable scans before submission? Train against these tasks rather than an assumed fixed number of practice scans.
- Ownership costs: Obtain a dated local quotation covering hardware, computing, training, replacement tips, batteries, repairs, optional software and support. Record actual scan, rescan, adjustment and remake time before estimating a return on investment.
- Records and continuity: Agree who can access patient data, how files are retained and exported, and how the practice will continue if the device, network or service is unavailable.
Automated alignment, margin suggestions and diagnostic aids should be assessed by their specific task and validation. Review a proposed margin against the acquired record; a plausible line can still be wrong. A percentage described only as “AI accuracy” is not enough to compare an algorithm with a clinician or to establish a treatment benefit.
The best choice is a supported workflow that your team can verify for its intended cases. Keep the benefits that digital acquisition can provide, while measuring the outcomes that matter: usable records, dependable laboratory communication, restoration checks and the patient’s experience. None follows automatically from the purchase of a particular scanner.
References and product documentation
Open the study and manufacturer sources
Clinical studies, laboratory experiments and manufacturer documentation serve different purposes. The study links below support the bounded findings discussed in the text; product documents describe particular configurations and should be checked against current local instructions.
- Ender A, Zimmermann M, Mehl A. Accuracy of complete- and partial-arch impressions of actual intraoral scanning systems in vitro. Int J Comput Dent. 2019;22:11–19. Primary study record.
- Son K, Lee KB. Effect of finish line locations of tooth preparation on the accuracy of intraoral scanners. Int J Comput Dent. 2021;24:29–40. Primary study record.
- Sakornwimon N, Leevailoj C. Clinical marginal fit of zirconia crowns and patients’ preferences for impression techniques using intraoral digital scanner versus polyvinyl siloxane material. J Prosthet Dent. 2017;118:386–391. Primary clinical study.
- Yuzbasioglu E, Kurt H, Turunc R, Bilir H. Comparison of digital and conventional impression techniques: evaluation of patients’ perception, treatment comfort, effectiveness and clinical outcomes. BMC Oral Health. 2014;14:10. Primary clinical study.
- Lee SJ, Jamjoom FZ, Le T, Radics A, Gallucci GO. A clinical study comparing digital scanning and conventional impression making for implant-supported prostheses: a crossover clinical trial. J Prosthet Dent. 2022;128:42–48. Primary clinical study.
- Jorba-García A, and colleagues. Accuracy of dental implant placement with or without the use of a dynamic navigation assisted system: a randomized clinical trial. Clin Oral Implants Res. 2023;34:438–449. Primary clinical study.
- Dentsply Sirona. Primescan brochure and CEREC system documentation.
- 3Shape. TRIOS 5. US FDA. K242103: TRIOS 5 L1P-1F indication for use.
- Align Technology. iTero Element Plus series and 5D/5D Plus user manual.
- Medit. i700 Wireless and wired i700.
- DEXIS. IS 3800 product documentation.