
CAD/CAM Ceramic Materials and Tooth Preparation: Product-Specific Clinical Planning
Can one preparation rule be applied to every CAD/CAM ceramic? Material selection and tooth preparation should be planned together. CAD/CAM can support restoration design within product-specific indications, but the material, restoration type and cementation method determine important requirements. This overview discusses selection and preparation principles; it does not report original clinical cases.
Which material structure are you selecting?
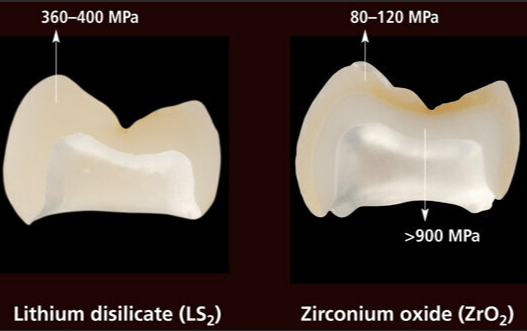
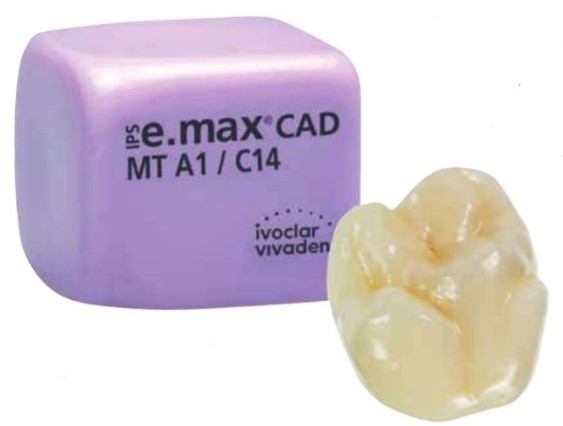
CAD/CAM materials are not interchangeable. Lithium disilicate glass-ceramics such as IPS e.max CAD are used for indicated veneers, inlays, onlays and crowns; bridge use is product- and site-limited. Ivoclar reports a mean biaxial flexural strength of 530 MPa after crystallization for IPS e.max CAD. Laboratory strength values depend on the test and product; they should not be treated as direct predictions of clinical longevity.
Zirconia products differ in composition, translucency, strength and permitted span. Select the exact grade before designing the restoration, and consult its current manufacturer instructions. The KATANA documentation distinguishes grade-specific minimum thicknesses and bridge indications.
VITA ENAMIC uses a polymer-infiltrated ceramic network. GC CERASMART270 is a glass-filled resin-based CAD/CAM material marketed as a hybrid ceramic. These materials do not have the same microstructure and require their own preparation, surface-treatment and cementation protocols.

How should preparation dimensions be chosen?
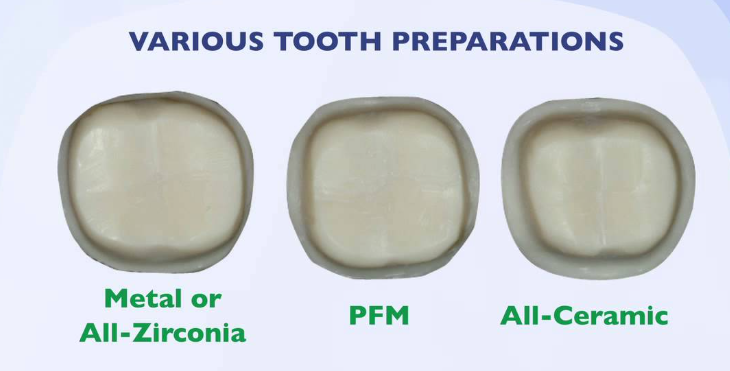
Set preparation dimensions from the current instructions for the exact material, restoration type and cementation method. Preserve sound tooth tissue while providing the required restoration thickness, rounded internal transitions, a readable finish line and adequate retention. Do not apply one numerical reduction range to all lithium disilicate, zirconia or resin-containing blocks.
For example, the CERASMART270 instructions specify a minimum wall thickness of 1.5 mm, 1.0 mm at margins, and 1.5 mm in occlusal pits, fissures and cusps. Restoration thickness is not automatically identical to tooth reduction. Feather-edge margins or greater taper should not be adopted simply because a restoration is milled; use a preparation design supported for the selected product.
What does the clinical outcome evidence establish?
A 2023 retrospective study of 25 patients receiving 25 CAD/CAM lithium-disilicate and 25 metal-ceramic crowns reported six-year cumulative survival of 96% and 90.8%, respectively. This small, specific cohort does not establish a universal survival rate. Material strength, manufacturing method and one study’s survival estimate should not be used as guarantees for another patient or restoration.
What should the dentist and laboratory plan together?
- For an anterior crown, assess underlying tooth color, restorative space, translucency, margin visibility and bonding conditions.
- For full-arch implant rehabilitation, also assess framework and connector design, prosthetic fit, occlusion and maintenance.
- Record the exact material and grade, restoration design and manufacturer instructions used for preparation and processing.
- Distinguish a digital preview from clinical verification of the restoration.
These are DDS educational planning considerations, not reported patient cases. A digital preview or material choice alone cannot guarantee shade matching or restoration survival.
Product examples and their boundaries


Does a digital workflow automatically produce a better restoration?
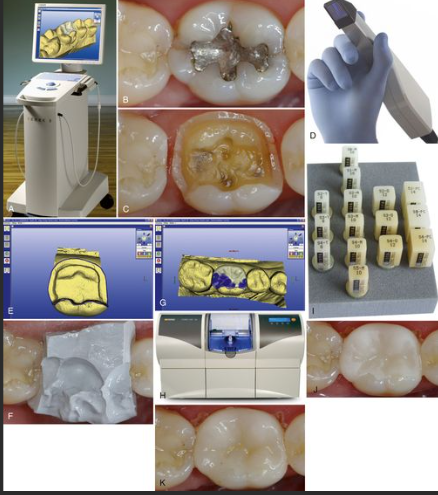
Chairside production can reduce visits in selected cases; laboratory workflow and visit count depend on the case. Digital records aid communication, while skilled clinical and laboratory shade assessment remains important. Fit depends on preparation, acquisition, design and manufacturing in both digital and conventional workflows. Strength depends on material, design and processing.
AI-assisted design and additive ceramic manufacturing are areas of continuing development. Their clinical value requires product-specific validation rather than an assumption of better longevity. Outcomes depend on the clinical indication, exact material, preparation quality, manufacturing, cementation and follow-up.